
| Download the amazing global Makindo app: ✅ Means NICE/National Guidelines 2026 compliant Android | Apple | |
|---|---|
| MEDICAL DISCLAIMER: Educational use only. Not for diagnosis or management. See below for full disclaimer. |
Asthma ✅
Current UK guidance: Chronic asthma — AIR/MART and objective diagnosis
- For newly diagnosed asthma at age 12 or above, offer as-needed low-dose ICS/formoterol (anti-inflammatory reliever, AIR) rather than SABA-only treatment; check the specific inhaler licence and formulary.
- If control remains inadequate, step up to low-dose then moderate-dose MART as appropriate; assess inhaler technique, adherence, exposure, exacerbations and objective markers before increasing treatment.
- Confirm asthma with objective tests where possible (blood eosinophils or FeNO, then bronchodilator reversibility, peak flow variability or bronchial challenge as required); tests can be less sensitive after ICS treatment.
- These statements relate to long-term asthma management. Acute severe asthma is a separate emergency pathway; do not apply the AIR maintenance algorithm to an unstable attack.
Reference: BTS/NICE/SIGN NG245 (checked 2026-10-30). This is a targeted evidence-linked teaching update; the historic article below still requires full clinical reconciliation. Follow local protocols and the current BNF for prescribing.
Related Subjects: |Asthma |Cystic Fibrosis |Bronchiolitis |Sweat Test |Acute Severe Asthma |Exacerbation of COPD |Pulmonary Embolism |Cardiogenic Pulmonary Oedema |Pneumothorax |Tension Pneumothorax |Respiratory (Chest) infections Pneumonia |Fat embolism |Hyperventilation Syndrome |ARDS |Respiratory Failure |Vocal Cord Dysfunction / Inducible Laryngeal Obstruction (ILO)
📖 Definition
- Asthma is a chronic inflammatory airway disorder with variable symptoms and variable expiratory airflow limitation (often reversible, but may become partly fixed with remodelling).
- Typical symptoms: episodic wheeze 🎶, cough, chest tightness, breathlessness; often worse at night/early morning and triggered by viruses, allergens, cold air, smoke or exercise.
💡 High-yield Asthma Acronyms to remember
- SABA = Short-Acting Beta2-Agonist quick reliever. e.g. salbutamol
- SAMA = Short-Acting Muscarinic Antagonist such as ipratropium. Used particularly in acute severe asthma alongside SABA.
- LABA = Long-Acting Beta2-Agonist e.g. formoterol or salmeterol. Usually used with inhaled corticosteroid
- ICS = Inhaled Corticosteroid. Preventer therapy that reduces eosinophilic airway inflammation and lowers the risk of exacerbations.
- PEF = bedside expiratory airflow measure using peak flow meter
- BDR = Bronchodilator Reversibility in spirometry
- FeNO = Fractional Exhaled Nitric Oxide eosinophilic/type 2 inflammation marker. Marker of type 2/eosinophilic airway inflammation. Can support asthma diagnosis and may predict steroid responsiveness.
- MART = Maintenance And Reliever Therapy one ICS/formoterol inhaler for maintenance + relief
- AIR = Anti-Inflammatory Reliever as-needed ICS/formoterol reliever strategy
🧬 Pathophysiology (bronchospasm and inflammation)
- Airway inflammation → oedema + mucus + bronchial hyperresponsiveness → airflow limitation and air-trapping.
- Common phenotype: Type 2 inflammation (eosinophilic/IgE-mediated): IL-4/5/13 → IgE switching + eosinophils → inflammation and exacerbation risk.
- Chronic poor control can cause airway remodelling (smooth muscle hypertrophy, goblet cell hyperplasia, subepithelial fibrosis) → less reversibility over time.
🫁 Types of asthma
- Extrinsic (allergic / atopic) asthma: commonly begins in childhood and is associated with type I hypersensitivity. It is driven by IgE-mediated immune responses to allergens such as house dust mite, pollen, animal dander, or mould. Patients often have a personal or family history of eczema, allergic rhinitis, or other atopic disease.
- Intrinsic (non-allergic) asthma: not clearly linked to atopy or a specific external allergen and is more likely to begin in adulthood. Triggers may include viral infections, cold air, exercise, stress, air pollution, gastro-oesophageal reflux, or irritants. The underlying problem is still chronic airway inflammation and bronchial hyper-responsiveness, even without an obvious allergic mechanism.
💡 In practice, this division is helpful for understanding pathophysiology, but many patients show overlap. Asthma is now better understood as a heterogeneous inflammatory airway disease with different phenotypes, including allergic, non-allergic, eosinophilic, and exercise-induced patterns.
⚡ Triggers & Risk Factors
- 🌫️ Tobacco smoke (including passive), pollution, cold air, strong odours, damp/mould.
- 🌿 Allergens: house dust mite, pets, pollens; consider ABPA if difficult asthma + Aspergillus sensitisation features.
- 🦠 Viral URTIs (major trigger), exercise, stress.
- 💊 NSAIDs/aspirin (esp. with nasal polyps), non-selective β-blockers.
- 🏭 Occupational asthma: suspect if adult onset + improves on days off/holidays (e.g., flour, isocyanates, cleaning agents).
🩺 Core Assessment (every consultation)
- Confirm diagnosis with objective testing where possible (don’t rely on symptoms alone).
- Control: daytime symptoms, night waking, activity limitation, reliever use, and exacerbations (oral steroids/ED/hospital).
- Risk: prior ICU/ventilation, frequent oral steroid courses, poor adherence, incorrect technique, smoking exposure, comorbidities.
- Comorbidities that worsen control: rhinitis/sinusitis, reflux, obesity, anxiety, OSA; consider vocal cord dysfunction, bronchiectasis.
Objective tests used to support an asthma diagnosis include: bronchodilator reversibility (BDR) with an FEV1 increase of ≥12% and ≥200 mL from baseline (or ≥10% of predicted), peak expiratory flow (PEF) variability ≥20% over 2 weeks, and FeNO ≥50 ppb in adults (or ≥35 ppb in children aged 5–16). Obstructive spirometry may support the diagnosis, but FEV1/FVC <0.70 alone does not confirm asthma, because obstruction can occur in other diseases such as COPD. Always interpret test results alongside a suggestive clinical history and remember that prior inhaled corticosteroid treatment can make spirometry and FeNO appear more normal.
🔎 Diagnosis - Adults (objective test–driven)
- Start with clinical suspicion (variable symptoms + triggers) then confirm objectively.
- Step 1 (Type 2 markers): measure blood eosinophils OR FeNO.
- Diagnose asthma if eosinophils are above lab reference range OR if FeNO ≥ 50 ppb and history suggests asthma.
- Step 2 (airflow variability): spirometry with bronchodilator reversibility (BDR).
- Diagnose if FEV1 increases by ≥12% and ≥200 mL (or ≥10% predicted) after bronchodilator.
- If spirometry is delayed/unavailable: PEF diary twice daily for 2 weeks.
- Diagnose if PEF variability ≥20% (amplitude % mean).
- If tests are negative but suspicion remains high: refer for specialist assessment (e.g., bronchial challenge testing) and consider alternative diagnoses.
👶 Diagnosis - Children aged 5–16
- Use objective testing where possible (symptoms alone are not enough).
- FeNO first (if available): diagnose if FeNO ≥35 ppb with suggestive history.
- If FeNO not raised/unavailable: perform spirometry with BDR; if delayed, use PEF variability; consider allergy testing (skin prick/IgE/eosinophils) as supportive evidence.
- Children under 5: diagnosis is often clinical + response to treatment with careful review; always reconsider alternative diagnoses (e.g., viral episodic wheeze, airway anomalies, aspiration).
🧪 Baseline & “rule-out” Investigations
- FBC (eosinophils), FeNO (if available), spirometry/PEF as above.
- CXR is usually normal in asthma; consider if atypical features, focal signs, fever, haemoptysis, suspected pneumothorax, or poor response.
- Allergy testing if allergic phenotype suspected and results would change management (avoidance, rhinitis treatment, ABPA work-up).
🧠 Differential Diagnoses (don’t miss)
- COPD (progressive symptoms, smoking history, less variability; fixed obstruction).
- Inducible laryngeal obstruction / vocal cord dysfunction (inspiratory noise, throat tightness, poor response to bronchodilator).
- Heart failure (“cardiac wheeze”), pulmonary embolism, bronchiectasis, foreign body, dysfunctional breathing/anxiety.
🚑 Treatment of Acute Severe Asthma
Acute severe asthma is a medical emergency. Give oxygen, bronchodilators, and systemic steroids promptly, and reassess frequently. Escalate early if there are features of life-threatening asthma, poor response to initial treatment, rising carbon dioxide, exhaustion, or reduced consciousness.
🔎 Recognise severity
- Acute severe asthma (adult) is suggested by any of:
- PEF 33–50% of best or predicted
- Respiratory rate ≥25/min
- Heart rate ≥110/min
- Unable to complete sentences in one breath
- Life-threatening asthma features include:
- PEF <33%
- SpO2 <92%
- Silent chest, cyanosis, poor respiratory effort
- Hypotension, arrhythmia, exhaustion
- Confusion, drowsiness, coma
- Normal or raised PaCO2
⚡ Immediate treatment
- Give oxygen to maintain saturations 94–98%.
- Give high-dose inhaled/nebulised salbutamol promptly.
- Usually 5 mg nebulised, driven by oxygen if needed
- If milder or able to use an inhaler: repeated doses via MDI + spacer can also be effective
- Add ipratropium bromide in acute severe or life-threatening attacks.
- Typical adult dose: 500 micrograms nebulised
- Give steroids early.
- Prednisolone 40–50 mg orally as soon as possible
- If unable to swallow: hydrocortisone 100 mg IV
📈 Monitoring and reassessment
- Check PEF, pulse, respiratory rate, SpO2, ability to speak, and work of breathing.
- Repeat assessment frequently after initial bronchodilator treatment.
- Perform ABG if SpO2 is <92%, if the patient looks exhausted, or if life-threatening asthma is suspected.
- A normal or raised PaCO2 in acute asthma is worrying and may indicate impending respiratory failure.
🧪 If poor response or severe attack
- Repeat nebulised salbutamol as needed.
- Continue/add nebulised ipratropium.
- Consider IV magnesium sulfate:
- 1.2–2 g IV over 20 minutes in adults with acute severe or life-threatening asthma not responding well to initial therapy
- Seek senior / critical care / anaesthetic support early if worsening, exhausted, hypercapnic, or deteriorating despite treatment.
🚨 Indications for ICU / urgent senior escalation
- Deteriorating PEF
- Persisting or worsening hypoxia
- Hypercapnia or acidosis
- Exhaustion, feeble respiration, silent chest
- Drowsiness, confusion, reduced consciousness
- Respiratory arrest or need for ventilatory support
🏥 Discharge and follow-up
- Do not discharge until clearly improving and safe.
- Ensure the patient has:
- An ICS-containing preventer inhaler
- Inhaler technique checked
- A personalised asthma action plan
- Smoking cessation support if relevant
- Follow-up arranged after the attack
💡 Practical memory aid: Oxygen + Salbutamol + Ipratropium + Steroids, then reassess quickly. If response is poor, think magnesium, ABG, and early ICU/senior escalation.
🎯 Long-Term Management - Principles
- Address fundamentals before stepping up: confirm diagnosis, correct technique, adherence, trigger reduction, and treat comorbidities.
- Provide a Personalised Asthma Action Plan (PAAP) and teach when/how to escalate and when to seek urgent help.
- Arrange structured follow-up: at least annual review and after any exacerbation.
💊 Acute Asthma Management (UK, BTS/NICE/SIGN NG245) Age > 12
| Step | When | Treatment | Key notes |
|---|---|---|---|
| 1 | Newly diagnosed asthma | AIR: low-dose Inhaled corticosteroid + formoterol used as needed | Reliever contains steroid + fast-onset LABA (formoterol) to treat bronchospasm + inflammation together. |
| 2 | Highly symptomatic at presentation or severe exacerbation history | Low-dose MART (maintenance and reliever Inhaled corticosteroid/formoterol) | Single-inhaler maintenance and reliever; simplifies plan and reduces attacks. |
| 3 | Not controlled on AIR | Low-dose MART | Check adherence/technique and triggers first. |
| 4 | Not controlled on low-dose MART | Moderate-dose MART | Review after step-up; minimise oral steroid exposure. |
| 5 | Persistent poor control on moderate-dose MART | Check Type 2 markers; consider add-ons and specialist referral | If FeNO/eosinophils raised → refer for severe asthma pathway (e.g., biologics). If not raised → consider trials of LTRA or LAMA. |
Children 5–11 years (stepwise)
- Stepwise approach includes paediatric low-dose ICS with reliever, step-up with add-ons and (in selected children able to use regimen safely) consideration of MART pathways per NG245 algorithm for 5–11.
- Always check technique/adherence and address triggers before escalating.
Children under 5
- Often symptom-pattern driven (viral episodic wheeze vs multiple-trigger wheeze); reassess diagnosis frequently.
- Typical approach: reliever therapy plus trial of regular paediatric low-dose ICS when indicated; consider LTRA trial in selected cases and stop if ineffective.
🧼 Non-pharmacological Management
- Smoking cessation (including household smoking); reduce damp/mould exposure; optimise rhinitis (intranasal steroid + antihistamine as needed).
- Vaccination and infection-avoidance advice in line with UK policy (flu/COVID as appropriate).
- Weight management, activity advice, and breathing pattern support where relevant.
🫁 Inhaler Technique - Practical, High-Yield
- Always observe technique (don’t just ask). Re-check at every review and after any exacerbation.
- Metered-Dose Inhaler (MDI) basics:
- Shake well → breathe out fully → seal lips → start slow deep breath and press once → continue slow deep inhale → hold breath ~10 seconds → wait ~30–60 sec between puffs.
- Common errors: firing too early/late, inhaling too fast, not shaking, not holding breath.
- Spacer (strongly preferred with ICS MDI):
- Attach inhaler → press 1 puff into spacer → take slow deep breath (or 5 tidal breaths in children) → repeat for each puff (one puff at a time).
- Clean spacer monthly (warm water + detergent), air-dry (reduces static), replace per manufacturer guidance.
- Dry Powder Inhaler (DPI):
- Load dose correctly → breathe out away from device → fast and deep inhale → hold breath ~10 seconds.
- Common errors: exhaling into device (clumps powder), inhaling too gently, poor seal.
- After any ICS dose: rinse mouth / brush teeth to reduce oral thrush and dysphonia.
🧾 Personalised Asthma Action Plan (PAAP) - what it must include
- Daily preventer plan (what to take when well) and how to check/track control.
- Worsening symptoms plan (what to increase, how often, and when to review).
- Emergency plan: clear red-flags and when to call 999/attend ED.
- For AIR/MART users: written instructions on using the ICS/formoterol inhaler as reliever during deterioration and thresholds for urgent care.
📅 Monitoring & Follow-up
- Primary care review at least annually and after any asthma exacerbation.
- At each review: confirm diagnosis if uncertain, assess control/risk, check technique + adherence, update PAAP, and rationalise inhalers.
- Consider PEF monitoring for people with poor perception of airflow limitation, frequent exacerbations, or for occupational patterns.
📚 NICE-aligned References
- NICE NG245 (BTS/NICE/SIGN): Asthma-diagnosis, monitoring and chronic asthma management (incl. Algorithms B/C/D/E).
- NICE CKS: Asthma-follow-up and acute exacerbation management.
- BNF (NICE): Acute asthma treatment summary.
Additional related clinical topics
Acute Severe Asthma (Status Asthmaticus)✅
⚠️ Prevention is key: All patients at risk of severe exacerbations should have an individualised plan 📋 to manage deterioration early with short-acting beta-agonists (SABA), oral steroids, and clear instructions to seek urgent medical help.
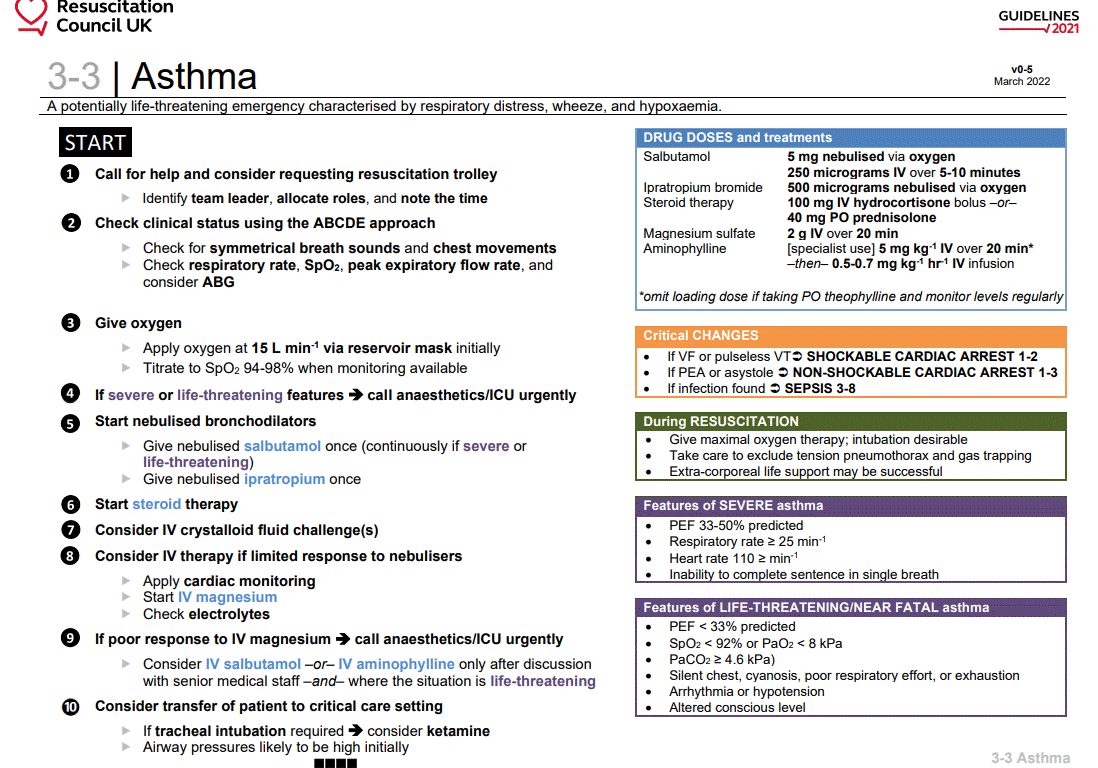
| 🚨 Initial Status Asthmaticus Management Summary |
|---|
|
📊 Assessing Severity in Adults (BTS/SIGN SIGN 158)
| Severity | Key Clinical Features | PEF (% best or predicted) | SpO₂ on air |
|---|---|---|---|
| Moderate exacerbation | Talking in sentences • No features of acute severe asthma | >50% | ≥92% |
| Acute severe asthma | Any one of: RR ≥25/min • HR ≥110/min • Unable to complete sentences in one breath | 33–50% | ≥92% |
| Life-threatening asthma | Any one of: SpO₂ <92% • PEF <33% • Silent chest • Cyanosis • Poor respiratory effort • Arrhythmia • Hypotension • Exhaustion • Confusion • Coma | <33% | <92% |
| Near-fatal asthma | Raised PaCO₂ and/or requiring mechanical ventilation | Variable | Variable |
👶 Children – Severity (same principles, age-adjusted)
- Use paediatric early warning score (PEWS) + BTS traffic-light system
- Life-threatening signs in children: SpO₂ <92%, silent chest, poor effort, hypotension, exhaustion, altered consciousness
- Clinical advice: Children can decompensate faster – involve senior paediatrician/anaesthetist early
🩻 Investigations & Monitoring – Clinical Advice
- PEF (if able) and continuous SpO₂, RR, HR
- ABG only if life-threatening features or not responding after 1 hour of treatment. A “normal” PaCO₂ (4.6–6.0 kPa) in a tachypnoeic distressed patient is ominous (indicates fatigue and impending failure). Rising PaCO₂ or acidosis = immediate senior/ICU discussion.
- CXR NOT routine – only if suspected pneumothorax, consolidation, pneumomediastinum, or life-threatening asthma
- U&E (watch potassium – salbutamol drives it down)
🚑 Initial Management – All Patients (Clinical Pearls)
- ABC approach • Sit upright • High-flow oxygen titrated to SpO₂ 94–98% (use Venturi if COPD overlap suspected)
- Continuous monitoring – never leave the patient unattended (even during transfer)
- Reassure calmly – anxiety worsens symptoms
- Clinical advice: If the patient cannot speak or is exhausted, prepare for advanced airway support immediately
💊 Pharmacological Management (BTS/SIGN SIGN 158)
Moderate exacerbation (PEF >50%)
- Salbutamol 4–10 puffs via spacer (or nebuliser 5 mg) – repeat every 15–30 min as needed
- Prednisolone 40–50 mg PO daily for at least 5 days (continue usual preventer ICS)
- Clinical advice: Good response = PEF >75% after 1 hour + stable → consider discharge with clear plan
Acute severe or life-threatening asthma
- Oxygen titrated to SpO₂ 94–98%
- Nebulised salbutamol 5 mg – give back-to-back (every 15 min) or continuous nebuliser until improvement or side effects appear
- Add nebulised ipratropium 500 micrograms (every 4–6 hours in severe cases)
- Systemic steroids: prednisolone 40–50 mg PO OR hydrocortisone 100 mg IV stat, then 100 mg IV 6-hourly if unable to swallow
- IV magnesium sulphate 2 g over 20 minutes (first-line add-on – give early in life-threatening cases)
- Senior/ICU review within 15–30 minutes for life-threatening features
🔴 Escalation if Poor Response – Practical Advice
- Repeat nebulisers + magnesium (already given)
- IV salbutamol infusion only on specialist advice (monitor lactate and potassium)
- Aminophylline infusion NOT routine – only if consultant decision
- Clinical advice: Prepare for intubation if: exhaustion, drowsiness, rising PaCO₂, respiratory arrest, or SpO₂ falling despite maximal therapy
Special Populations – Important Clinical Advice
- Pregnancy: Treat aggressively – uncontrolled asthma is more dangerous than medicines. Steroids and salbutamol are safe. Continue usual preventer. Involve obstetric team early.
- Obese patients: May need higher doses or longer nebuliser time; consider vocal cord dysfunction as differential.
- Smokers/vapers: Higher risk of poor response – give smoking cessation advice and nicotine replacement in hospital.
🏡 Discharge Criteria & Planning – Practical Checklist
- PEF >75% best/predicted • No acute severe features • Stable on usual therapy for 1–2 hours
- Continue Prednisolone 40–50 mg for 5 days total (no taper needed)
- Check and correct inhaler technique BEFORE discharge (critical step – most readmissions are technique-related)
- Prescribe regular preventer ICS-based therapy (no SABA monotherapy)
- Provide written Personalised Asthma Action Plan (PAAP) + PEF meter if appropriate
- Arrange follow-up: GP/asthma nurse within 48 hours (after ED attendance) or 2 weeks (after admission)
- Safety-netting advice: Return immediately if worsening, unable to speak, or PEF falling
- Review triggers (viral, allergens, occupational, NSAIDs) and offer smoking cessation support
📚 Official References (2026)
- BTS/SIGN British Guideline on the Management of Asthma – SIGN 158 (2019 with 2024/2025 pathway updates)
- NICE NG244 Asthma: diagnosis, monitoring and chronic asthma management (2024)
- NICE NG245 Acute asthma management summary
- BTS Acute Asthma Audit recommendations 2025
This is an educational summary only. Always follow your local hospital protocol, trust guidelines and obtain senior advice. Early escalation saves lives. Last updated March 2026.
| The content on this website is provided for educational and informational purposes only to support exam preparation (e.g., MLA, MRCP, USMLE) and learning. This is NOT medical advice, diagnosis, treatment, or professional guidance. It does not replace consultation with a qualified healthcare professional, official guidelines (e.g., NICE, GMC, BNF), or supervised clinical practice. Always verify information with current, authoritative sources. Makindo and its contributors accept no liability for any reliance on this content, including errors, omissions, or any resulting harm, loss, or consequences. By using this site, you agree to these terms. |
|
|
Categories
- Acute Medicine
- Anaesthetics and Critical Care
- Cardiology
- Collections
- Dermatology
- Differentials
- Drugs
- Electrocardiogram
- Emergency Medicine
- Endocrinology
- ENT
- Foundation Doctors
- Gastroenterology
- General Practice
- Genetics
- Geriatric Medicine
- Haematology
- Hepatology
- Immunology
- Infectious Diseases
- Investigations
- Microbiology
- Nephrology
- Neurology
- Neurosurgery
- Obstetrics Gynaecology
- Oncology
- Ophthalmology
- Oral Medicine and Dentistry
- OSCE
- Paediatrics
- Palliative
- Pharmacology
- Physiology
- Procedures
- Psychiatry
- Public Health
- Radiology
- Respiratory
- Resuscitation
- Revision Topics
- Rheumatology
- Stroke
- Surgery
- Toxicology
- Trauma and Orthopaedics
- Urology
- Vascular Surgery