Urinary Obstruction
Urinary retention is the inability to empty the bladder completely. Acute retention is painful, sudden and usually needs immediate catheterisation; chronic retention develops gradually with high post-void residuals and often minimal discomfort. Think “plumbing” (outflow obstruction), “power” (detrusor failure/neuropathy), and “poison” (drugs like anticholinergics and opioids) as a quick diagnostic lens.
Key Definitions 📘
- Acute urinary retention (AUR): Sudden painful inability to void with a palpable/scan-visible bladder.
- Chronic urinary retention (CUR): Persistently raised post-void residual (commonly >300–500 mL) with weak stream, nocturia, UTIs or overflow incontinence.
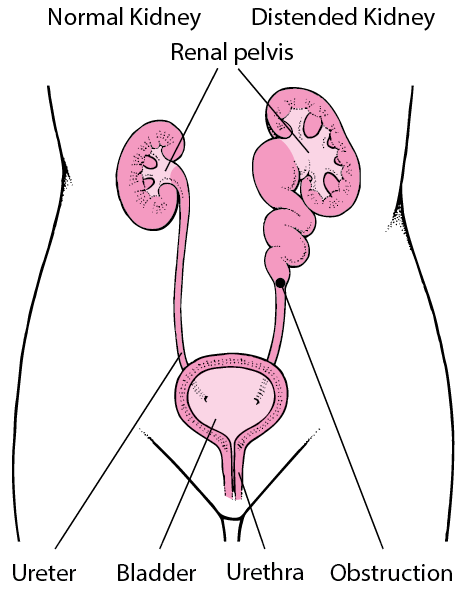
- High-pressure retention: CUR with hydronephrosis and/or AKI due to back-pressure-nephrology/urgent urology input.
Pathophysiology 🧠
Detrusor contraction (parasympathetic S2–S4) must overcome outlet resistance at the bladder neck, prostate and urethra. Obstruction (e.g., BPH, urethral stricture) increases afterload; chronic overdistension causes myogenic failure and impaired sensation. Neurological lesions (diabetes, spinal cord disease, cauda equina) disrupt afferent or efferent pathways; medicines with anticholinergic or sympathomimetic effects inhibit detrusor and tighten the outlet.
Common Causes (By Group) 🧩
- Obstructive: BPH, prostate cancer, urethral stricture, bladder neck stenosis, severe constipation/faecal impaction, pelvic organ prolapse.
- Infective/Inflammatory: Prostatitis, severe urethritis, vulvovaginitis with oedema.
- Neurological: Diabetic autonomic neuropathy, MS, Parkinson’s, stroke, spinal cord compression/cauda equina, postoperative neuraxial anaesthesia.
- Drugs 💊: Anticholinergics (oxybutynin, TCAs), opioids, alpha-agonists, antihistamines, benzodiazepines, antipsychotics, NSAIDs (fluid retention), severe alcohol intoxication.
- Post-operative/Peri-partum: Pain, immobility, anaesthetic effects; postpartum bladder dysfunction.
Red Flags 🚩 (Act Urgently)
- Back pain, saddle anaesthesia, bilateral sciatica, new leg weakness, or loss of anal tone/sphincter-suspect cauda equina.
- Fever, rigors, sepsis with retention (possible obstructed infected system).
- AKI, hyperkalaemia, or hydronephrosis on ultrasound (high-pressure retention).
- Gross haematuria with clot retention.
History & Examination 🧾
- Symptoms: Time course, pain, lower urinary tract symptoms (hesitancy, poor stream, nocturia), overflow dribbling, incontinence, UTIs.
- Context: New meds, alcohol, constipation, recent surgery/anaesthesia, pregnancy/post-partum, neurological disease.
- Exam: Distended bladder, DRE (tone; prostate size/tenderness), pelvic exam if relevant, focused neurology (perineal sensation, reflexes), hydration status.
Immediate Assessment in A&E/Acute Care 🏥
- Bladder scan: If >400–600 mL with inability to void, proceed to catheterisation. >800–1000 mL suggests chronic/high-risk retention.
- Urinalysis: Infection/haematuria.
- Bloods: U&Es/creatinine, FBC, CRP if infective picture.
- Ultrasound kidneys/bladder: If AKI, hydronephrosis, recurrent retention, or high residuals.
Initial Management - Acute Retention 🚑
- Analgesia (avoid excessive anticholinergic burden).
- Urethral catheter (usually 12–16 Ch). If difficult (stricture, BPH with false passages) or failed attempts, seek urology help; consider suprapubic catheter if urethral contraindicated.
- Drain and measure immediate volume; monitor for post-obstructive diuresis (polyuria >200 mL/h for >2–3 h) → replace fluids, check U&Es.
- Alpha-blocker (e.g., tamsulosin 400 micrograms once daily) to improve Trial Without Catheter (TWOC) success.
- Antibiotics only if clear infection (do not treat asymptomatic bacteriuria in catheterised patients).
Trial Without Catheter (TWOC) 🔄
- Typically attempt after 24–72 hours on an alpha-blocker if AUR due to presumed BPH and no red flags.
- Void trial with post-void residual measurement. If fails, re-catheterise and refer urology.
Chronic Retention - Principles 🧭
- Confirm persistently raised PVR (often >300–500 mL) and assess for complications: UTIs, hydronephrosis, renal impairment.
- Outflow obstruction (e.g., BPH): Alpha-blocker ± 5-alpha-reductase inhibitor (finasteride 5 mg daily) if enlarged prostate and medium-to-long-term plan.
- Detrusor underactivity/neuropathic bladder: Timed voiding, double voiding, and clean intermittent self-catheterisation (CISC) if suitable.
- Long-term catheter if CISC unsuitable; review complications (UTIs, blockage, stones) and consider suprapubic route for comfort/sexual function.
Female & Special Populations 👩⚕️
- Women: Pelvic organ prolapse, postoperative retention, urethral stricture (rare), vulval oedema; early pelvic floor referral.
- Pregnancy/post-partum: Prompt bladder scanning and catheterisation; avoid unnecessary anticholinergics.
- Neurogenic bladder: MS, Parkinson’s, spinal injury-multidisciplinary management; urodynamics often needed.
When to Refer to Urology 📮
- Recurrent retention or failed TWOC.
- High-pressure retention (hydronephrosis/AKI).
- Suspected malignancy, significant haematuria, recurrent UTIs or stones.
- Urethral stricture/trauma or catheterisation failure.
Catheter Tips 🧰
- Most adults: 12–16 Ch Foley; use smaller sizes in strictures. Avoid repeated forceful attempts.
- Document drained volume, time, and any haematuria or pain.
- Consider leg bag by day and night bag at night; educate on hygiene and red flags.
Complications to Watch ⚠️
- Post-obstructive diuresis with electrolyte loss.
- UTIs, epididymo-orchitis, prostatitis.
- Hydronephrosis, CKD progression.
- Bladder atony with persistent high residuals.
- Clot retention after haematuria/instrumentation.
Prescribing Nuggets (UK) 💡
- Tamsulosin 400 micrograms once daily (review for postural hypotension; caution in cataract surgery-IFIS risk).
- Finasteride 5 mg once daily (only if enlarged prostate; teratogenic to male fetus-avoid handling crushed tablets).
- Avoid routine bethanechol; limited benefit and adverse effects.
- Review and deprescribe offending agents (anticholinergics, opioids) when feasible.
Safety Netting & Discharge 🏡
- Return urgently for fever, rigors, anuria, worsening pain, haematuria with clots, or confusion.
- If discharged with catheter: provide catheter care leaflet, community nursing support, and a dated plan for TWOC or urology clinic.
- Arrange repeat U&Es if large initial volumes or AKI.
Teaching Pearls for Juniors 🎓
- Scan first if unsure-palpation is insensitive in obesity.
- Don’t miss cauda equina-back pain + retention + saddle numbness = MRI and urgent spinal referral.
- Measure what you drain and watch urine output post-catheter; diuresis can be profound.
- Start an alpha-blocker in likely BPH-related AUR to improve TWOC success.
- Think chronic when volumes are huge but pain is minimal-check kidneys and consider urodynamics/urology review.
- Case 1 - Acute painful retention in BPH (drug-triggered) 🚑: A 74-year-old man develops 8 hours of suprapubic pain and inability to void after starting co-codamol and chlorphenamine for a cold; exam shows a distended tender bladder, DRE reveals a smooth enlarged prostate, bladder scan ~900 mL, UA negative; management is immediate urethral Foley catheter (14–16 Ch) with documentation of drained volume, start tamsulosin 400 micrograms nocte and stop anticholinergics/opioids, then plan a TWOC at 48–72 h with safety-netting for post-obstructive diuresis.
- Case 2 - Chronic painless high-pressure retention with AKI 🧪: A 79-year-old with months of nocturia, weak stream and overflow dribbling is admitted with lethargy; bladder scan pre-void 1.5 L, post-void 1.2 L, U&Es show creatinine 250 μmol/L (baseline 120), renal ultrasound demonstrates bilateral hydronephrosis; manage with prompt catheterisation and close monitoring for post-obstructive diuresis (hourly urine, fluid/electrolyte replacement), review medicines (stop NSAIDs), start alpha-blocker ± finasteride if prostate enlarged, arrange urology follow-up for definitive outflow treatment and nephrology input if renal recovery is incomplete.
- Case 3 - Neurogenic retention from cauda equina syndrome 🚩: A 56-year-old presents with acute back pain radiating to both legs, new saddle anaesthesia, reduced anal tone and urinary retention (scan 700 mL) after lifting a heavy box; immediate priorities are red-flag recognition and escalation for urgent MRI spine and spinal surgery review, avoid repeated traumatic catheter attempts (single gentle attempt then consider suprapubic if needed), start IV dexamethasone if advised locally, and document neurological findings meticulously while arranging time-critical decompression to maximise bladder and sphincter recovery.
