
| Download the amazing global Makindo app: ✅ Means NICE/National Guidelines 2026 compliant Android | Apple | |
|---|---|
| MEDICAL DISCLAIMER: Educational use only. Not for diagnosis or management. See below for full disclaimer. |
Arrhythmias
Arrhythmias are disturbances of cardiac rhythm ⚡, ranging from benign ectopic beats to life-threatening ventricular fibrillation. They result from disordered impulse generation or conduction, and can cause palpitations, syncope, stroke, heart failure, or sudden cardiac death 💔. Management depends on the type of arrhythmia, its haemodynamic impact, and underlying structural or systemic disease.
🔬 Pathophysiology
- Automaticity: Abnormal pacemaker activity from atrial, nodal, or ventricular tissue.
- Triggered activity: Afterdepolarisations (e.g., in long QT, digoxin toxicity).
- Re-entry circuits: Common mechanism in SVT, atrial flutter, and VT.
- Conduction abnormalities: AV nodal disease, bundle branch block, accessory pathways.
- Systemic contributors: Electrolyte imbalance (K⁺, Mg²⁺, Ca²⁺), ischaemia, hypoxia, drugs, thyroid disease.
⚡ Common Types of Arrhythmia
- Atrial Fibrillation (AF) ❤️: Irregularly irregular rhythm; stroke risk ×5.
- Atrial Flutter 🌀: Macro–re-entry tachycardia, sawtooth ECG pattern.
- Supraventricular Tachycardia (SVT) 🚀: AVNRT/AVRT, abrupt onset palpitations.
- Ventricular Tachycardia (VT) ⚠️: Wide-complex, often post-MI, risk of degeneration to VF.
- Ventricular Fibrillation (VF) 💥: Chaotic rhythm, no cardiac output, requires immediate defibrillation.
- Bradyarrhythmias 🐢: Sinus node dysfunction or AV block; risk of syncope/sudden death.
- Premature Beats 💥: PACs and PVCs, benign if isolated but frequent PVCs may cause cardiomyopathy.
📋 Clinical Assessment
- History: Palpitations, dizziness, syncope, chest pain, breathlessness; triggers (alcohol, caffeine, stress).
- Examination: Irregular/fast/slow pulse; signs of HF, murmurs, thyrotoxicosis.
- ECG: Gold standard for rhythm diagnosis; 12-lead whenever possible.
- Ambulatory monitoring: Holter, event recorder, implantable loop recorder.
- Echocardiography: Defines structural substrate (LV function, valves, atrial size).
- Blood tests: U&E, Mg²⁺, Ca²⁺, TFTs, troponin, digoxin level.
🛡️ Management Principles
Step 1: Assess stability Unstable = shock the patient (cardioversion/defibrillation). Stable = consider drugs, vagal manoeuvres, or elective cardioversion.
❤️ Atrial Fibrillation (AF) / Atrial Flutter
- Acute unstable AF/flutter: Immediate synchronised DC cardioversion (up to 3 attempts).
- Rate control (first-line in most, esp. >65 or minimal symptoms): - Beta-blockers (bisoprolol, metoprolol). - Rate-limiting calcium-channel blockers (diltiazem, verapamil). - Digoxin (less effective in high sympathetic tone; use in sedentary/heart failure). - Target resting HR <110 bpm (lenient control, per RACE II trial).
- Rhythm control (younger, symptomatic, first episode): - Pharmacological cardioversion: flecainide, amiodarone. - Electrical cardioversion (sedation required). - Catheter ablation (increasing role, esp. for paroxysmal AF).
- Anticoagulation: - Assess with CHA₂DS₂-VASc (stroke risk) & HAS-BLED (bleeding risk). - DOACs (apixaban, rivaroxaban, dabigatran, edoxaban) are first-line in UK unless contraindicated. - Warfarin if mechanical valve or severe mitral stenosis. - Anticoagulation reduces stroke risk by 60–70%.
🚀 Supraventricular Tachycardia (SVT)
- Stable acute SVT: Vagal manoeuvres (Valsalva, carotid sinus massage with caution).
- If unsuccessful: IV adenosine 6 mg, then 12 mg if needed (contraindicated in asthma).
- Alternatives: IV verapamil or beta-blockers.
- Recurrent SVT: Electrophysiology study + catheter ablation (curative in >90%).
⚠️ Ventricular Tachycardia (VT)
- Unstable VT: Immediate synchronised cardioversion.
- Pulseless VT: Defibrillation + ALS protocol.
- Stable VT: - IV amiodarone (preferred). - Lidocaine alternative if ischaemic.
- Secondary prevention: ICD implantation (reduces sudden cardiac death by ~50%).
- Adjuncts: Beta-blockers, ablation for recurrent VT storm.
💥 Ventricular Fibrillation (VF)
- Immediate defibrillation (unsynchronised shock).
- CPR until defibrillator ready; survival drops 10% per minute delay.
- Adrenaline every 3–5 min; amiodarone 300 mg after 3rd shock.
- Post-resuscitation: ICD, address reversible causes (4 Hs & 4 Ts).
🐢 Bradyarrhythmias
- Acute symptomatic bradycardia: IV atropine 500 micrograms (repeat up to 3 mg).
- If ineffective: isoprenaline/adrenaline infusion, transcutaneous pacing.
- Long-term: Permanent pacemaker (sinus node disease, Mobitz II, complete AV block).
🤖 Device Therapy
- Pacemaker: Sinus node dysfunction, AV block, symptomatic bradycardia.
- ICD: Survivors of VF/VT arrest, LVEF ≤35% with ischaemic/non-ischaemic cardiomyopathy.
- Cardiac Resynchronisation Therapy (CRT): HF with LVEF ≤35%, QRS ≥130 ms, symptomatic despite optimal medical therapy.
🩺 Additional Considerations
- Correct reversible causes: Electrolytes, hypoxia, thyroid disease, drugs (QT-prolonging agents).
- Lifestyle: Reduce alcohol, caffeine, stimulants; weight loss and BP control reduce AF burden.
- Special populations: - Post-MI patients → beta-blockers, ACE inhibitors, ICD consideration. - Pregnancy → avoid teratogenic drugs (use labetalol, sotalol; avoid amiodarone if possible).
📊 High-Yield Summary Table
| Arrhythmia | ECG Features | Acute Management | Long-Term Management |
|---|---|---|---|
| Atrial Fibrillation ❤️ | Irregularly irregular, no P waves | Rate/rhythm control, anticoagulation if unstable → DC cardioversion | Rate vs rhythm strategy; anticoagulation; ablation in selected cases |
| SVT 🚀 | Regular, narrow-complex | Vagal manoeuvres → adenosine → cardioversion | Catheter ablation (curative); beta-blockers/CCBs |
| Ventricular Tachycardia ⚠️ | Wide-complex tachycardia | Unstable → cardioversion; Stable → amiodarone | ICD; beta-blockers; ablation for VT storm |
| Ventricular Fibrillation 💥 | Chaotic, no complexes | Defibrillation + CPR + ALS drugs | ICD; secondary prevention |
| Bradyarrhythmia 🐢 | Slow HR, sinus pauses, AV block | Atropine → pacing if unstable | Permanent pacemaker |
📝 Conclusion
Arrhythmia management rests on rapid recognition, assessing haemodynamic stability, and tailoring therapy to the arrhythmia mechanism. Always correct reversible factors, use drugs and devices appropriately, and refer for ablation or ICD when indicated. In AF, stroke prevention through anticoagulation is as vital as rhythm control. In VT/VF, ICDs and defibrillation save lives. Understanding both acute and chronic management is key to safe, evidence-based practice.
Disclaimer: Educational content only. Always follow current ESC, AHA, and Resus Council UK guidelines in clinical practice.
Additional related clinical topics
Broad Complex Tachycardia
📖 Broad-Complex Tachycardia (BCT)
- Broad QRS = QRS duration >120 ms (>3 small squares).
- BCT = tachycardia with broad QRS complexes. The big fork in the road is regular vs irregular.
- Why it matters: VT can rapidly deteriorate into VF/cardiac arrest, so early, safe decision-making is crucial.
📊 Causes of BCT (regular vs irregular)
| Pattern | Likely causes | High-risk “don’t miss” |
|---|---|---|
| Regular BCT |
|
|
| Irregular BCT |
|
|
🩺 First 30 seconds: assess stability
- Unstable features: shock, syncope, ongoing chest pain/MI features, acute heart failure/pulmonary oedema, severe hypotension.
- If unstable with a pulse: synchronised DC cardioversion (sedate if conscious and time allows).
- If pulseless VT/VF: follow ALS cardiac arrest (defibrillation + CPR).
🔎 ECG clues that favour VT
| ECG/clinical clue | Why it points to VT | What you do with it |
|---|---|---|
| AV dissociation (P waves “march through” independently) | Atria and ventricles are being driven by different pacemakers | Treat as VT; urgent senior/cardiology input |
| Capture beats (a single narrow QRS during BCT) | Occasional supraventricular impulse conducts to ventricle amid VT | Strong VT support |
| Fusion beats (hybrid QRS morphology) | Simultaneous ventricular activation from sinus + ventricular focus | Strong VT support |
| Known structural heart disease / prior MI | Scar-related re-entry VT is common in this group | Lower your threshold to shock / treat as VT |
🧪 Investigations (don’t delay treatment if unstable)
- 12-lead ECG (if stable) + continuous monitoring.
- Bloods: U&E, Mg, Ca, glucose, FBC, troponin (if ACS possible) ± ABG/VBG if unwell.
- Echo later to assess LV function/structural disease (especially if VT suspected).
⚕️ Management table (Resus Council UK–aligned approach)
| Scenario | Immediate action | Key “don’ts” |
|---|---|---|
| Unstable BCT with a pulse |
|
|
| Stable regular BCT |
|
|
| Stable irregular BCT |
|
|
| Torsades de pointes (polymorphic VT + prolonged QT) |
|
|
🧠 Rhythm snapshots (high-yield)
- Monomorphic VT: usually regular, broad QRS, often post-MI scar-related; can present with palpitations, syncope, or shock.
- VF / pulseless VT: cardiac arrest rhythms → ALS shockable pathway (defib + CPR).
- Pre-excited AF (WPW): irregularly irregular, very fast, varying QRS morphologies; avoid AV-nodal blockers and seek urgent expert help.
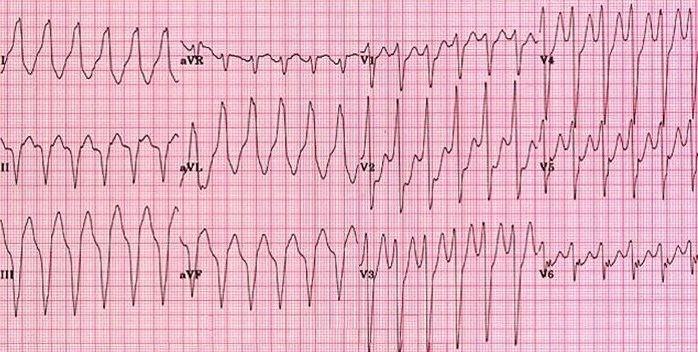
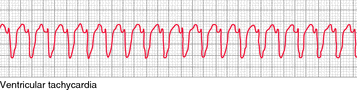
🌟 Clinical teaching point: The danger in BCT is mislabelling VT as “SVT with BBB” and giving the wrong therapy. When myocardium is ischaemic or scarred, re-entry circuits make VT more likely; the longer it runs, the more likely it becomes haemodynamically unstable. That’s why UK algorithms prioritise stability → shock if needed → antiarrhythmic strategy, rather than perfect rhythm diagnosis first.
📚 References (UK + core)
- Resuscitation Council UK: Tachycardia (with pulse) algorithm (peri-arrest guidance, cardioversion/antiarrhythmic approach).
- Resuscitation Council UK: Peri-arrest arrhythmias (ALS educational material).
- ESC: 2022 guidelines on ventricular arrhythmias & sudden cardiac death prevention (context for VT risk in structural heart disease).
Torsades de pointes TdP (Polymorphic VT)
⚡ Torsades de Pointes (Polymorphic VT): Occurs in repetitive, non-sustained paroxysms but can degenerate into VF. 💉 First-line: IV magnesium 8 mmol (2 g) bolus over 10–15 mins in 50–100 ml 5% dextrose or saline. ❌ Avoid amiodarone. Correct K/Mg/Ca. Consider pacing, isoprenaline (except congenital LQTS), and defibrillation if unstable.
📖 About
- Coined by Dessertenne in 1966.
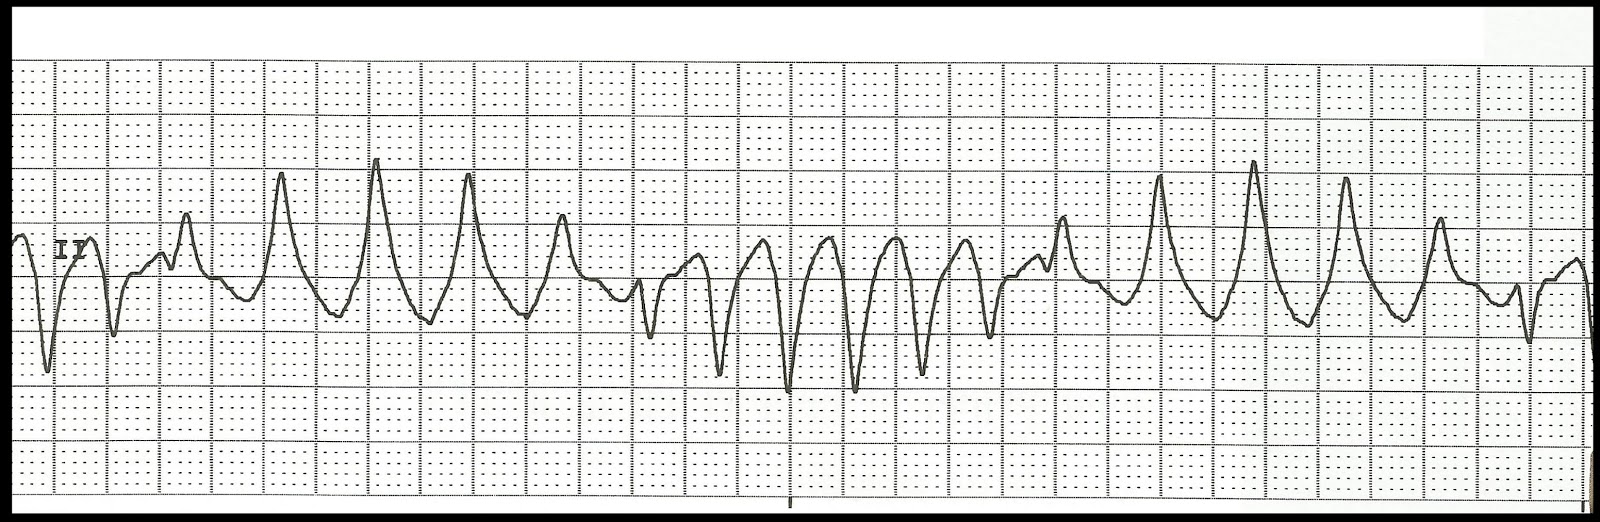
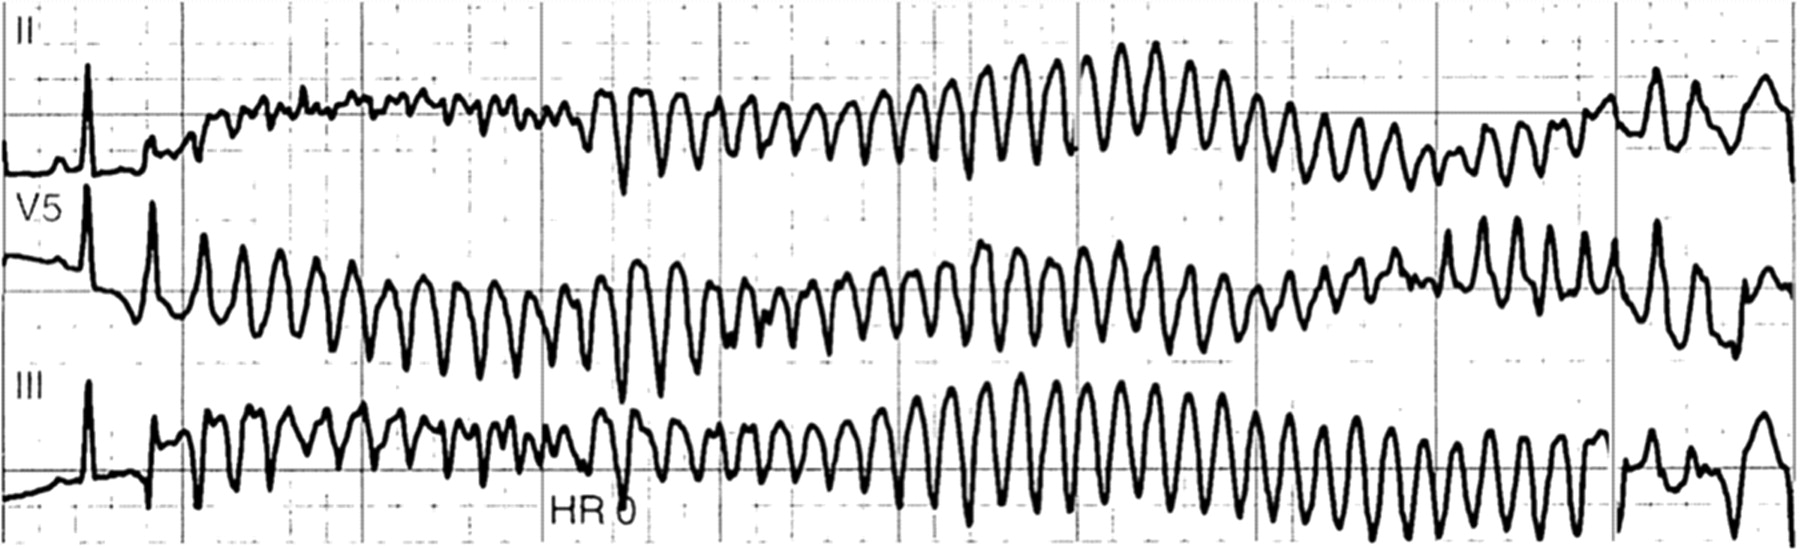
- A polymorphic ventricular tachycardia with the QRS axis “twisting around the baseline.”
- Commonly associated with prolonged QTc >460 ms.
- Drug-associated risk varies - see www.qtdrugs.org.
📌 Definition
- Polymorphic VT with continuously changing QRS axis.
- Seen in congenital or acquired Long QT syndrome.
- Often due to inhibition of the HERG potassium channel.
🖥️ Electrocardiogram
🧬 Genetics
- LQT1 & LQT2 → slow potassium channels.
- LQT3 → sodium channel defects.
- LQT4–12 → rarer subtypes.
- Congenital long QT: autosomal dominant, more pronounced in females.
📊 Epidemiology
- Females 2–3x more likely to develop TdP.
- Drug-induced QT prolongation more common in women.
🩺 Clinical
- Occurs in bursts, often self-terminating.
- Symptoms: presyncope, syncope, hypotension, pulmonary oedema.
- May deteriorate to sustained VT/VF → cardiac arrest.
⚠️ Risk Factors
- Congenital: Romano-Ward (AD), Jervell-Lange-Nielsen (AR + deafness).
- Acquired: electrolyte disorders (↓K, ↓Ca, ↓Mg), medications, bradycardia.
- Other: baseline ECG abnormalities, renal or liver impairment, female sex.
💊 Causes of Acquired Long QT
- Electrolyte/metabolic: hypokalaemia, hypocalcaemia, hypomagnesaemia, hypothyroidism, hypothermia.
- Drugs: amiodarone, disopyramide, flecainide, erythromycin, terfenadine, TCAs, quinidine, lithium, phenothiazines. 👉 Always check in BNF.
🔎 Investigations
- FBC, U&E, Mg, Ca, TFTs, troponin if ACS suspected.
- ECG: twisting QRS, prolonged QTc often >500 ms.
- Echocardiogram: rule out structural heart disease.
🛠️ Management
- Stop offending drugs (esp. amiodarone, class I/III antiarrhythmics).
- IV magnesium sulphate: 8 mmol (2 g) bolus → then 72 mmol (18 g) over 24 hrs.
- Pacing (atrial > ventricular) if bradycardia-dependent TdP.
- IV isoprenaline: useful for acquired TdP but contraindicated in congenital LQTS.
- Defibrillation if unstable.
- Congenital LQTS: beta-blockers mainstay; consider ICD or left stellate ganglion block for refractory cases.
- Acquired LQTS: beta-blockers contraindicated (bradycardia worsens risk).
📚 References
💡 Teaching Pearl: TdP is always a “red flag rhythm.” Think: correct electrolytes, stop QT-prolonging drugs, give magnesium, pace or shock if needed.
| The content on this website is provided for educational and informational purposes only to support exam preparation (e.g., MLA, MRCP, USMLE) and learning. This is NOT medical advice, diagnosis, treatment, or professional guidance. It does not replace consultation with a qualified healthcare professional, official guidelines (e.g., NICE, GMC, BNF), or supervised clinical practice. Always verify information with current, authoritative sources. Makindo and its contributors accept no liability for any reliance on this content, including errors, omissions, or any resulting harm, loss, or consequences. By using this site, you agree to these terms. |
|
|
Categories
- Acute Medicine
- Anaesthetics and Critical Care
- Cardiology
- Collections
- Dermatology
- Differentials
- Drugs
- Electrocardiogram
- Emergency Medicine
- Endocrinology
- ENT
- Foundation Doctors
- Gastroenterology
- General Practice
- Genetics
- Geriatric Medicine
- Haematology
- Hepatology
- Immunology
- Infectious Diseases
- Investigations
- Microbiology
- Nephrology
- Neurology
- Neurosurgery
- Obstetrics Gynaecology
- Oncology
- Ophthalmology
- Oral Medicine and Dentistry
- OSCE
- Paediatrics
- Palliative
- Pharmacology
- Physiology
- Procedures
- Psychiatry
- Public Health
- Radiology
- Respiratory
- Resuscitation
- Revision Topics
- Rheumatology
- Stroke
- Surgery
- Toxicology
- Trauma and Orthopaedics
- Urology
- Vascular Surgery