Hodgkin vs Non-Hodgkin Lymphoma:
Related Subjects:
|Hodgkin Lymphoma
|Non Hodgkin Lymphoma
|Diffuse large B-cell lymphoma
|Intravascular large B-cell lymphoma
|Mantle cell lymphoma
|Marginal Zone Lymphoma
|Gastric (MALT) Lymphoma
|Primary CNS Lymphoma (PCNSL)
|Burkitt's lymphoma
|Follicular Lymphoma
|Hodgkin vs Non-Hodgkin Lymphoma:
Lymphoma is a group of cancers arising from lymphocytes (B cells, T cells, or NK cells). It is broadly divided into Hodgkin lymphoma (HL), characterised by Reed–Sternberg cells, and non-Hodgkin lymphoma (NHL), which includes many subtypes ranging from indolent to highly aggressive.
✅ UK guidance framing: in primary care, think first about recognition and urgent referral. Unexplained lymphadenopathy should raise suspicion for lymphoma; splenomegaly particularly increases concern for NHL. Associated symptoms such as fever, drenching night sweats, weight loss, pruritus, and shortness of breath strengthen suspicion.
🧬 Pathophysiology
- Lymphomas arise from acquired genetic abnormalities in lymphocytes, causing clonal proliferation, impaired apoptosis, and disordered immune-cell behaviour.
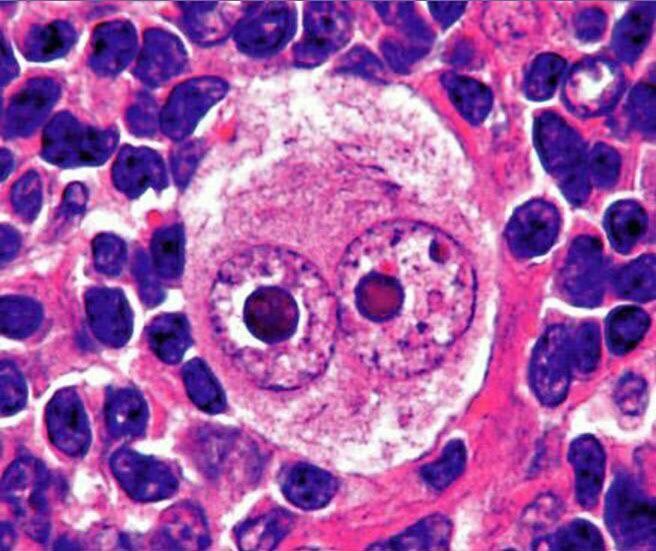
- Hodgkin lymphoma classically contains Reed–Sternberg cells within a prominent inflammatory background.
- Non-Hodgkin lymphoma is biologically heterogeneous and may arise from B cells, T cells, or NK cells; extranodal disease is more common than in HL.
⚖️ Hodgkin vs Non-Hodgkin Lymphoma
| Feature |
Hodgkin Lymphoma 🟢 |
Non-Hodgkin Lymphoma 🔵 |
| Pathology |
Reed–Sternberg cells present. |
Reed–Sternberg cells absent; multiple B-, T-, and NK-cell subtypes. |
| Typical pattern |
Often orderly/contiguous nodal spread. |
Often non-contiguous spread; extranodal disease more common. |
| Presentation |
Painless lymphadenopathy, often cervical; may have B symptoms, pruritus, or mediastinal disease. |
Painless lymphadenopathy or splenomegaly; may have B symptoms or site-specific symptoms depending on subtype and site. |
| Age |
Often shows a bimodal age distribution. |
Can occur at any age, but incidence rises with age overall. |
| Behaviour |
Often highly treatable and frequently curable. |
Variable: may be indolent, aggressive, or highly aggressive depending on subtype. |
🚩 When to suspect lymphoma
- Unexplained lymphadenopathy, especially if persistent.
- Unexplained splenomegaly (particularly concerning for NHL).
- B symptoms: fever, drenching night sweats, unexplained weight loss.
- Other concerning features: pruritus, shortness of breath, mediastinal symptoms, fatigue, recurrent infections, bruising, or site-specific symptoms from extranodal disease.
- Alcohol-induced node pain is a rare but classic association with HL.
🔍 Diagnosis
- Excision biopsy is generally preferred as the first diagnostic procedure when lymphoma is suspected.
- If excision biopsy is not suitable because procedural risk outweighs benefit, a needle core biopsy may be considered.
- If a core biopsy is non-diagnostic and feasible, excision biopsy should be pursued.
- Diagnosis depends on histology, immunophenotyping, and subtype classification.
- Staging may involve CT or PET-CT, and additional tests such as bone marrow biopsy may be required in selected cases.
📊 Staging
- Staging is usually described using the Ann Arbor system:
- Stage I: single lymph node region or single extralymphatic site.
- Stage II: 2 or more nodal regions on the same side of the diaphragm.
- Stage III: nodal disease on both sides of the diaphragm.
- Stage IV: disseminated extranodal involvement such as bone marrow, liver, or other organs.
- B symptoms are commonly recorded because they have prognostic significance.
💊 Management
- Management is specialist-led and depends on subtype, stage, bulk of disease, symptoms, comorbidity, and patient fitness.
- Treatment may include chemotherapy, immunochemotherapy, radiotherapy, targeted therapy, stem cell transplantation, or in some cases active monitoring (“watch and wait”).
- Supportive care is important, including infection prevention, fertility discussion where relevant, and management of complications such as tumour lysis syndrome.
🩺 Clinical Pearls
- Do not reassure persistent unexplained lymphadenopathy without follow-up or further assessment.
- Generalised lymphadenopathy, splenomegaly, or B symptoms should lower the threshold for urgent referral.
- Extranodal disease (for example GI tract, skin, CNS) is more suggestive of NHL than HL.
- Lymphoma may present with normal early blood tests, so normal FBC does not exclude it.
📚 Summary
👉 Lymphoma is a malignancy of lymphocytes.
🟢 HL is defined by Reed–Sternberg cells and often follows a more orderly nodal pattern.
🔵 NHL is a heterogeneous group with variable behaviour, from indolent to highly aggressive.
📌 In UK practice, NICE emphasis is on early recognition, suspected cancer referral, tissue diagnosis with appropriate biopsy, and subtype-specific specialist management.
Additional related clinical topics
Hodgkin Lymphoma ✅
📖 About
- Hodgkin lymphoma is a cancer of B-lymphocyte lineage.
- It usually arises in lymph nodes and often spreads in a relatively contiguous nodal pattern.
- It is much less common than non-Hodgkin lymphoma.
- It is highly treatable, and many patients are cured.
📊 Epidemiology
- There are around 2,000 new cases per year in the UK.
- HL accounts for roughly 10% of lymphomas in the UK.
- It has a bimodal age distribution, with one peak in younger adults and another in older adults.
- Incidence and mortality are slightly higher in men.
🧬 Pathophysiology & Aetiology
- HL arises from abnormal germinal-centre/post-germinal-centre B cells.
- The malignant Reed–Sternberg cells are few in number, but they release cytokines and chemokines that recruit a dense inflammatory infiltrate.
- This inflammatory microenvironment explains many systemic symptoms, including fever, weight loss, night sweats, pruritus, and raised ESR.
- EBV is associated with a proportion of cases, particularly in mixed cellularity disease and in immunosuppressed patients.
⚠️ Risk Factors
- 👶 Age: most common in younger adults, with a second later-life peak.
- ♂️ Sex: slightly more common in men overall.
- 👨👩👧 Family history: modestly increases risk.
- 🦠 EBV infection: associated with some cases.
- 🛡️ Immunodeficiency: including HIV and post-transplant immunosuppression.
🔬 Histological Subtypes
- Classical Hodgkin lymphoma:
- Nodular sclerosis: most common; often affects young adults and commonly involves the mediastinum.
- Mixed cellularity: more often linked with EBV and immunosuppression.
- Lymphocyte-rich: less common; generally favourable prognosis.
- Lymphocyte-depleted: rare and more aggressive.
- Nodular lymphocyte-predominant Hodgkin lymphoma (NLPHL) is a distinct entity and behaves differently from classical HL.
📍 Staging (Ann Arbor)
| Stage | Description |
|---|
| I | Single lymph node region or single extralymphatic site |
| II | 2 or more nodal regions on the same side of the diaphragm |
| III | Nodal disease on both sides of the diaphragm, possibly with splenic involvement |
| IV | Diffuse/disseminated extranodal involvement (for example marrow, liver, lung) |
| A | No B symptoms |
| B | B symptoms present |
🔥 B Symptoms
- 🌡️ Fever
- 😰 Drenching night sweats
- ⚖️ Unexplained weight loss of more than 10%
- These reflect a systemic inflammatory response and have staging/prognostic significance.
🧑⚕️ Clinical Features
- Painless lymphadenopathy is the commonest presenting feature.
- Nodes are often firm, rubbery, and non-tender.
- Common sites: cervical, supraclavicular, mediastinal, and axillary nodes.
- General symptoms: fatigue, fever, night sweats, weight loss.
- Pruritus can occur and may precede diagnosis.
- Mediastinal disease may cause cough, chest discomfort, or breathlessness.
- Alcohol-related node pain is a rare but classic association.
- Splenomegaly may be present.
🧪 Investigations
- Blood tests: FBC, U&E, LFTs, ESR, CRP, LDH, urate, and baseline virology as guided by treatment planning.
- Excisional lymph node biopsy is the preferred diagnostic test.
- Histology typically shows Reed–Sternberg cells; classical HL is often CD15+ and CD30+.
- PET-CT is central to staging and response assessment in modern HL practice.
- CT may also be used for anatomical staging.
- Bone marrow biopsy is now selective rather than routine in all patients.
- Baseline echocardiogram or equivalent cardiac assessment is important if anthracyclines are planned; pulmonary assessment may be needed if bleomycin is being considered.
💊 Management
- Management is specialist-led and depends on stage, bulk of disease, symptoms, age, comorbidity, and fitness.
- Early-stage disease is often treated with short-course combination chemotherapy ± involved-site radiotherapy.
- Advanced disease is usually treated with systemic combination chemotherapy, with radiotherapy reserved for selected bulky or residual sites.
- Relapsed or refractory disease may be treated with salvage chemotherapy, autologous stem cell transplant, and/or newer agents such as brentuximab vedotin or PD-1 inhibitors.
- Supportive care includes fertility counselling, infection risk management, and treatment-toxicity monitoring.
💉 Treatment Pearls
- ABVD has been a longstanding backbone regimen in classical HL.
- Doxorubicin can cause cardiotoxicity; bleomycin can cause pulmonary toxicity.
- Older or frailer patients often need modified treatment because toxicity can outweigh benefit.
- Modern management increasingly uses response-adapted PET-guided strategies.
🩺 NICE/UK Primary Care Pearl
Think of Hodgkin lymphoma in any adult with unexplained lymphadenopathy, especially if there is fever, drenching night sweats, weight loss, pruritus, or shortness of breath. Normal initial blood tests do not exclude lymphoma.
📚 References
Non Hodgkin Lymphoma ✅
📖 About
- NHL is a group of lymphoid cancers with many biologically distinct subtypes.
- It may arise in lymph nodes, spleen, bone marrow, blood, or extranodal tissues such as the GI tract, skin, or CNS.
- Presentation and prognosis depend heavily on subtype and stage.
- Malignant lymphoma is an HIV indicator condition.
⚠️ When to suspect NHL
- Unexplained lymphadenopathy.
- Unexplained splenomegaly.
- Associated symptoms increasing suspicion: fever, drenching night sweats, weight loss, pruritus, shortness of breath.
- Extranodal symptoms may occur depending on site involved.
🧾 Types of NHL
- B-cell lymphomas:
- Diffuse large B-cell lymphoma (DLBCL)
- Follicular lymphoma
- MALT lymphoma / marginal zone lymphoma
- Mantle cell lymphoma
- Burkitt lymphoma
- CLL/SLL is usually classified separately in many teaching schemes but overlaps biologically with indolent lymphoid neoplasia.
- T-cell / NK-cell lymphomas:
- Peripheral T-cell lymphoma
- Cutaneous T-cell lymphoma
- Anaplastic large cell lymphoma
⚠️ Risk Factors
- Increasing age.
- Immunodeficiency, including HIV and post-transplant states.
- Autoimmune disease.
- Some chronic infections are linked to specific subtypes, for example H. pylori with gastric MALT lymphoma.
- Previous chemotherapy/radiotherapy may increase later haematological malignancy risk.
🧑⚕️ Clinical Features
- Painless persistent lymphadenopathy.
- B symptoms: fever, night sweats, weight loss.
- Splenomegaly or hepatosplenomegaly.
- Extranodal disease: GI, skin, CNS, marrow, testis, breast, kidney, adrenal, etc.
- Cytopenias may occur if marrow is involved.
- Raised LDH can suggest more proliferative disease.
📊 Staging
| Stage | Definition |
|---|
| I | Single lymph node region or single extranodal site |
| II | 2 or more nodal regions on the same side of the diaphragm |
| III | Nodal disease on both sides of the diaphragm |
| IV | Disseminated extranodal involvement, such as marrow or other organs |
| A | No B symptoms |
| B | B symptoms present |
🧪 Investigations
- Bloods: FBC, renal function, liver bloods, LDH, urate, and other baseline tests as guided by the clinical picture.
- Excision biopsy is generally preferred as the first diagnostic procedure.
- If excision biopsy is unsuitable because procedural risk outweighs benefit, needle core biopsy may be considered.
- If core biopsy is non-diagnostic, pursue excision biopsy if feasible.
- Histology, immunophenotyping, and molecular/cytogenetic testing help define subtype.
- CT or FDG-PET-CT may be used for staging depending on subtype and whether results will alter management.
- Bone marrow biopsy and lumbar puncture are used in selected cases, not universally.
- Offer/consider HIV testing because lymphoma is an HIV indicator condition.
🏃 Performance Status
- ECOG performance status helps assess fitness for treatment and prognosis.
💊 Management
- Management is subtype-specific and specialist-led.
- Treatment options may include watch and wait, radiotherapy, immunochemotherapy, targeted therapy, and stem cell transplantation.
- Localised stage IIA follicular lymphoma: local radiotherapy is first-line; selected asymptomatic patients may be observed if radiotherapy is unsuitable.
- Symptomatic stage III/IV follicular lymphoma: rituximab-based chemotherapy options are recommended by NICE.
- Gastric MALT lymphoma: treat H. pylori if present; eradication therapy is central to management.
- Mantle cell lymphoma and DLBCL: treatment depends on fitness, stage, and specialist protocol; transplant may be used in selected patients.
- Supportive care includes tumour lysis prevention where relevant, fertility discussion, infection prophylaxis/support, and clear follow-up planning.
🧠 CNS Risk in DLBCL
- NICE highlights increased CNS risk with involvement of the testis, breast, adrenal gland, or kidney.
- Risk may also be higher with raised LDH, age >60, ECOG ≥2, >1 extranodal site, or stage III/IV disease.
📚 References
