
| Download the amazing global Makindo app: ✅ Means NICE/National Guidelines 2026 compliant Android | Apple | |
|---|---|
| MEDICAL DISCLAIMER: Educational use only. Not for diagnosis or management. See below for full disclaimer. |
Cystic Fibrosis ✅
Related Subjects: |Cystic Fibrosis |Sweat Test |Osteoporosis |Malabsorption |Bronchiectasis |Pseudomonas infection (Pseudomonas aeruginosa) |Autosomal Recessive |Genetic Mutations |Clustered Regularly Interspaced Short Palindromic Repeats CRISPR
⚠️ Cystic Fibrosis (CF) is an autosomal recessive CFTR channel disorder causing impaired chloride transport → dehydrated secretions → impaired mucociliary clearance → chronic infection and inflammation. ✅ Diagnosis is based on clinical features and/or newborn screening plus evidence of CFTR dysfunction (for example, sweat chloride testing and genetic testing). 💡 With modern specialist care and CFTR modulators, median predicted survival in the UK now exceeds 50 years.
📖 About
- Inherited defect of the Cystic Fibrosis Transmembrane Conductance Regulator (CFTR) protein.
- Leads to abnormal salt and water transport across epithelial surfaces.
- Results in dehydrated, tenacious secretions causing airway obstruction, chronic infection, inflammation, and multisystem disease.
- Commonly affects the respiratory, gastrointestinal, endocrine, hepatobiliary, reproductive, and musculoskeletal systems.
🧬 Aetiology
- Autosomal recessive inheritance.
- CFTR gene is on chromosome 7q31.2.
- More than 2,000 CFTR variants have been described.
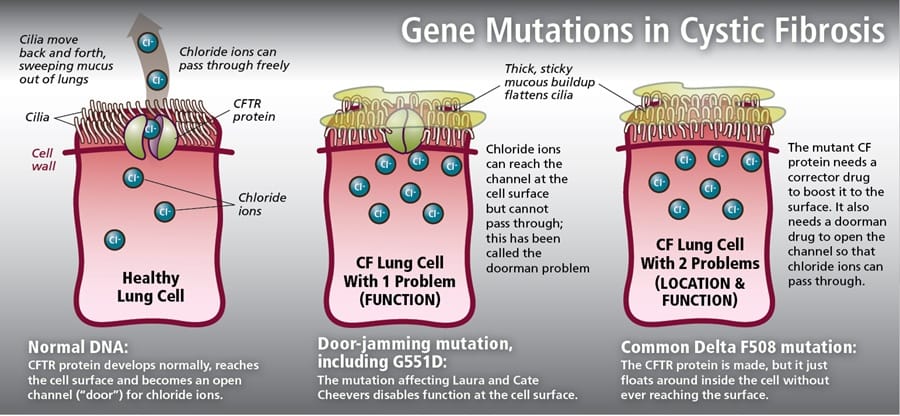
- F508del (ΔF508) is the most common pathogenic variant in the UK population.
- Genotype does not fully predict severity because phenotype is influenced by modifier genes, environment, infection burden, and treatment access.
- Incidence in the UK is approximately 1 in 2,500 live births; carrier frequency is around 1 in 25 in people of Northern European ancestry.
🧪 Gene Mutations & Effects
🔍 Diagnosis
- Often detected by newborn screening using raised immunoreactive trypsinogen (IRT), followed by confirmatory testing.
- Diagnosis is supported by clinical manifestations together with evidence of CFTR dysfunction.
- Sweat chloride ≥60 mmol/L is consistent with CF in the appropriate clinical context.
- 30–59 mmol/L is intermediate / borderline and needs further assessment.
- Genetic testing may identify 2 CF-causing CFTR variants.
- Additional physiological testing such as nasal potential difference or intestinal current measurement may be used in atypical or inconclusive cases.
🧪 Investigations
- Sweat chloride test: key diagnostic test; usually repeated or interpreted alongside genetics and clinical features.
- Genetic testing: mutation analysis helps confirm diagnosis and identify eligibility for CFTR modulator therapy.
- Pancreatic function: faecal elastase for pancreatic insufficiency.
- Respiratory assessment: spirometry, sputum or cough swab microbiology, chest imaging if indicated.
- Microbiology: monitor for Pseudomonas aeruginosa, Staphylococcus aureus, Haemophilus influenzae, and other pathogens.
- Endocrine screening: screen annually for CF-related diabetes; in children this is commonly with OGTT from age 10 years.
- Nutritional assessment: growth, BMI, fat-soluble vitamin status.
- Hepatobiliary review: LFTs and assessment for liver disease if indicated.
- Fertility assessment: semen analysis in adult males if needed; consider reproductive counselling.
🫁 Clinical Features (Respiratory)
- Persistent or recurrent cough.
- Recurrent chest infections.
- Wheeze and progressive airflow obstruction.
- Bronchiectasis due to chronic infection-inflammation cycles.
- Pseudomonas colonisation is associated with worse long-term lung outcomes.
- Chronic rhinosinusitis and nasal polyps are common.
- Complications include massive haemoptysis, pneumothorax, and respiratory failure.
🍽️ Clinical Features (Gastrointestinal / Nutritional)
- Meconium ileus in neonates.
- Pancreatic insufficiency causing malabsorption, steatorrhoea, abdominal distension, and failure to thrive.
- Distal intestinal obstruction syndrome (DIOS).
- Poor weight gain and fat-soluble vitamin deficiency.
- Hepatic steatosis, focal biliary cirrhosis, gallstones, and chronic liver disease may occur.
- CF-related diabetes (CFRD) becomes increasingly common with age.
🧍 Other System Features
- Clubbing.
- Low bone mineral density / osteoporosis.
- Arthropathy may occur.
- Male infertility is common, usually due to congenital bilateral absence of the vas deferens.
- Females may have reduced fertility, but many can conceive.
- Salty-tasting sweat is a classic clue.
📊 Summary of Testing
| Diagnostic Test | Description | Interpretation |
|---|---|---|
| 🧪 Sweat Chloride Test | Measures sweat chloride after pilocarpine iontophoresis | ≥60 mmol/L supports CF; 30–59 mmol/L intermediate; <30 mmol/L usually makes CF unlikely |
| 🧬 Genetic Testing | Identifies CFTR variants | 2 disease-causing variants support diagnosis |
| ⚡ Nasal Potential Difference | Assesses CFTR-dependent ion transport | Useful in atypical or indeterminate cases |
| 👶 Newborn IRT | Screening blood spot test | Raised result triggers confirmatory testing |
⚠️ Complications
- Chronic suppurative lung disease and bronchiectasis.
- Respiratory failure and need for transplant assessment in advanced disease.
- CFRD.
- Low bone mineral density / osteoporosis.
- Chronic liver disease and portal hypertension.
- Reduced fertility or infertility.
- Psychological burden, treatment fatigue, and reduced quality of life.
💊 Management
| Area | Interventions | Notes |
|---|---|---|
| Specialist care 🏥 | Management through a specialist CF multidisciplinary team | Core NICE principle |
| Airway clearance 🫁 | Chest physiotherapy, airway clearance techniques, oscillating PEP, exercise, nebulised therapies where indicated | Daily long-term treatment |
| Mucolytics 💨 | Dornase alfa; nebulised hypertonic saline where appropriate | Used to improve sputum clearance and reduce exacerbations |
| Antibiotics 💊 | Oral, inhaled, or IV antibiotics guided by symptoms, microbiology, and specialist advice | Long-term inhaled antibiotics may be used for chronic Pseudomonas |
| Macrolide therapy | Azithromycin may be used long term in selected patients | Can reduce exacerbation frequency and has anti-inflammatory effects |
| Nutrition 🍽️ | Pancreatic enzyme replacement therapy (PERT), high-energy diet, fat-soluble vitamin supplements | Essential for growth, lung health, and overall outcomes |
| CFTR modulators 🧬 | Examples include ivacaftor, lumacaftor/ivacaftor, tezacaftor/ivacaftor, and elexacaftor/tezacaftor/ivacaftor | Eligibility depends on genotype and commissioning arrangements |
| Complication management | Monitor and treat CFRD, liver disease, bone disease, sinus disease, fertility issues | Regular screening is important |
| Advanced disease | Assessment for lung transplantation when appropriate | Consider in progressive advanced lung disease |
| Psychosocial support ❤️ | Mental health support, counselling, education, transition planning, social support | Important because treatment burden is high |
📚 References
- NICE guideline NG78: Cystic fibrosis: diagnosis and management
- Cystic Fibrosis Trust UK Registry reports and standards of care
- Specialist CF centre / MDT guidance for ongoing management
| The content on this website is provided for educational and informational purposes only to support exam preparation (e.g., MLA, MRCP, USMLE) and learning. This is NOT medical advice, diagnosis, treatment, or professional guidance. It does not replace consultation with a qualified healthcare professional, official guidelines (e.g., NICE, GMC, BNF), or supervised clinical practice. Always verify information with current, authoritative sources. Makindo and its contributors accept no liability for any reliance on this content, including errors, omissions, or any resulting harm, loss, or consequences. By using this site, you agree to these terms. |
|
|
Categories
- Acute Medicine
- Anaesthetics and Critical Care
- Cardiology
- Collections
- Dermatology
- Differentials
- Drugs
- Electrocardiogram
- Emergency Medicine
- Endocrinology
- ENT
- Foundation Doctors
- Gastroenterology
- General Practice
- Genetics
- Geriatric Medicine
- Haematology
- Hepatology
- Immunology
- Infectious Diseases
- Investigations
- Microbiology
- Nephrology
- Neurology
- Neurosurgery
- Obstetrics Gynaecology
- Oncology
- Ophthalmology
- Oral Medicine and Dentistry
- OSCE
- Paediatrics
- Palliative
- Pharmacology
- Physiology
- Procedures
- Psychiatry
- Public Health
- Radiology
- Respiratory
- Resuscitation
- Revision Topics
- Rheumatology
- Stroke
- Surgery
- Toxicology
- Trauma and Orthopaedics
- Urology
- Vascular Surgery