Hypoglycaemia
Related Subjects: Type 1 DM
|Type 2 DM
|Diabetes in Pregnancy
|HbA1c
|Diabetic Ketoacidosis (DKA) Adults
|Hyperglycaemic Hyperosmolar State (HHS)
|Diabetic Nephropathy
|Diabetic Retinopathy
|Diabetic Neuropathy
|Diabetic Amyotrophy
|Maturity Onset Diabetes of the Young (MODY)
|Diabetes: Complications
|Hypoglycaemia
|Gold Score: Hypoglycaemia Awareness in Type 1 Diabetes
🚨 Hypoglycaemia Urgent Management. Also see
|Gold Score: Hypoglycaemia Awareness in Type 1 Diabetes
Capillary or Plasma Glucose < 3–4 mmol/L (≈72 mg/dL) |
- ⚡ Symptoms: Trembling, sweating, confusion, hunger, anxiety, coma, seizures.
- 🧠 Neuroglycopenia: Drowsiness, speech difficulty, odd behaviour, collapse.
- ❗ Severe: Coma when CBG <1.5 mmol/L. If GCS <9 or difficult to manage → call for senior help/Crash team.
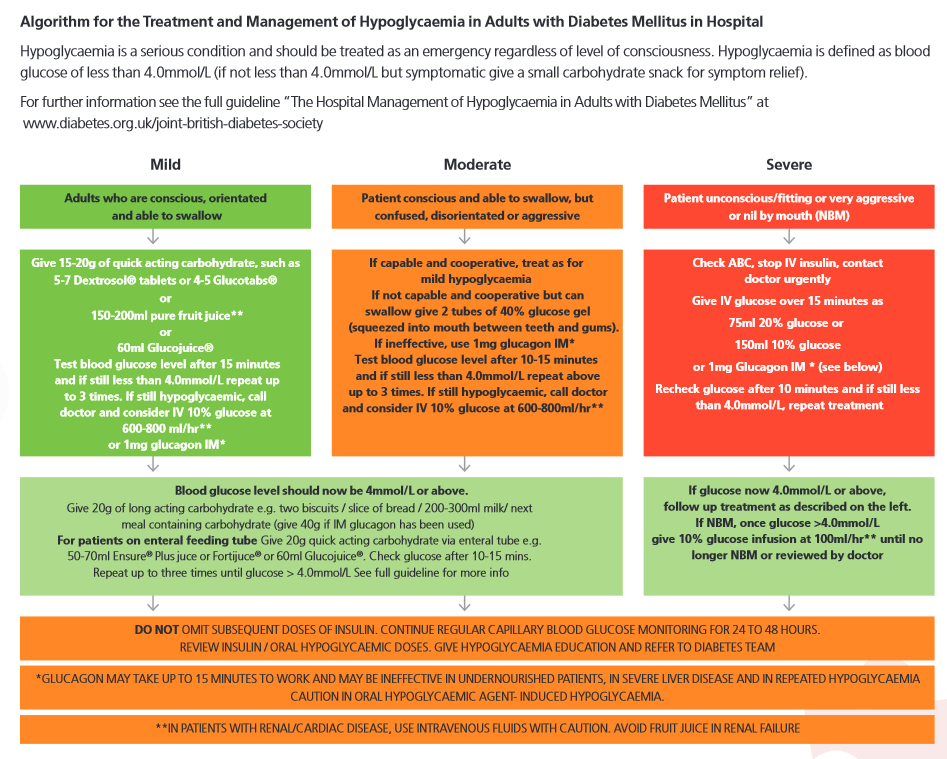
- 😊 Conscious & able to swallow: 4 Glucotabs OR Dextrogel OR 15–20 g rapid sugar (avoid diet drinks).
- 💉 Unconscious/unable to swallow:
- IV: 150 mL of 10% glucose (over 10–15 min).
- IM/SC: Glucagon 1 mg (intranasal where available).
⚠️ Less effective in malnutrition or liver failure.
- 🔁 Persisting hypoglycaemia: Infuse 10% glucose 1L over 4–6 h with CBG monitoring.
- 🕵️ Review cause: Missed meal? Sulfonylurea? Insulin error? Alcohol? Intercurrent illness?
|
📖 Introduction
- Hypoglycaemia is potentially fatal - delayed treatment risks irreversible brain injury.
- Most common cause: 💉 Insulin or sulfonylureas (missed meals, OD, deliberate self-harm).
⚠️ Think broadly: Addison’s disease, liver failure, alcohol binge without food, insulinoma, pituitary disease, quinine, severe sepsis, malaria.
🧪 Clinical Features
- 🤯 Autonomic: Sweating, tremor, palpitations, hunger, anxiety.
- 🧠 Neuroglycopenic: Confusion, odd behaviour, slurred speech, seizures, coma.
- 💥 May mimic stroke, seizure, delirium → always check CBG!
🧾 Whipple’s Triad
- Compatible symptoms/signs of hypoglycaemia.
- Documented low plasma glucose.
- Resolution after glucose correction.
🔍 Investigations
- Confirm lab glucose + CBG.
- Insulin & C-peptide (to distinguish endogenous vs exogenous insulin use).
- Consider: LFTs, renal profile, cortisol/ACTH, ±72-hour fast if unexplained.
💊 Management (Stepwise)
- 📏 Measure CBG: <3–4 mmol/L → act immediately.
- 🥤 If cooperative: 15–20 g rapid sugar (e.g., 150 mL pure juice). Recheck in 10–15 min. Repeat ×3 if still <4.
- 🍯 If uncooperative but safe swallow: 2 tubes of 40% glucose gel (e.g., Glucogel) buccally.
- 💉 If unable to swallow/unconscious:
- IV 150 mL 10% glucose (or 20/50% equivalents) → recheck after 10 min.
- IM/SC glucagon 1 mg (intranasal 3 mg if available).
- ⏳ Prolonged hypoglycaemia: IV infusion 10% glucose; monitor closely.
- 🍺 Alcohol/malnutrition: Give IV thiamine (Pabrinex) with glucose.
- 🔄 Aftercare: Prevent recurrence → adjust insulin/meds, review diet, diabetes specialist input.
📊 Causes (Mnemonics)
- Exogenous: Insulin, sulfonylureas, quinine, alcohol binge.
- Endogenous: Insulinoma, Addison’s, pituitary failure, severe sepsis.
- Misc: Critical illness, malnutrition, bodybuilders misusing insulin.
📑 References