
| Download the amazing global Makindo app: ✅ Means NICE/National Guidelines 2026 compliant Android | Apple | |
|---|---|
| MEDICAL DISCLAIMER: Educational use only. Not for diagnosis or management. See below for full disclaimer. |
Cryptococcus neoformans infections (Cryptococcal Infections)
Related Subjects: | Meningococcal Meningitis | Pneumococcal Meningitis | Listerial Meningitis |Herpes Simplex Encephalitis (HSV) |Acute Encephalitis |Toxoplasmosis |Lumbar Puncture |CSF Interpretation
💡 Key point: Cryptococcal meningitis can have surprisingly little CSF inflammation, particularly in advanced HIV. Opening pressure may be markedly raised and must be measured at lumbar puncture. Cryptococcal antigen (CrAg) in CSF is the key rapid diagnostic test. Raised intracranial pressure is itself an important cause of death and neurological disability and requires active treatment with therapeutic lumbar puncture.
📖 About
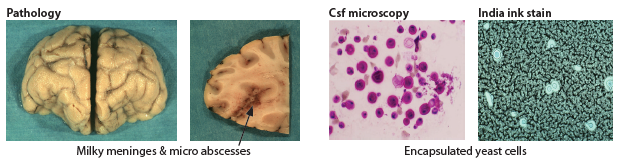
- Cryptococcosis is an invasive fungal infection caused mainly by the encapsulated yeasts Cryptococcus neoformans and Cryptococcus gattii.
- The polysaccharide capsule is a major virulence factor, helping the organism evade phagocytosis and host immune responses.
- Infection is usually acquired through inhalation from the environment, producing an initial pulmonary infection that may be asymptomatic.
- Haematogenous dissemination can subsequently occur, with a particular tropism for the central nervous system.
- CNS disease usually presents as a subacute meningitis or meningoencephalitis and is potentially fatal without treatment.
🌱 Source & Pathogenesis
- C. neoformans is widely distributed in soil and material contaminated by bird droppings, particularly pigeon guano.
- C. gattii is associated particularly with soil and certain trees and can cause disease in apparently immunocompetent people.
- Organisms are inhaled → pulmonary infection → survival within macrophages → haematogenous dissemination → penetration of the blood–brain barrier.
- Cryptococcus has marked neurotropism and may multiply extensively within the CSF.
- High organism burden interferes with CSF resorption at the arachnoid granulations, contributing to raised intracranial pressure (ICP).
⚠️ Who Is At Risk?
- Advanced HIV infection, especially CD4 <100 cells/mm³ and particularly <50 cells/mm³.
- Solid-organ or haematopoietic stem-cell transplantation.
- Haematological malignancy.
- Prolonged corticosteroid or other immunosuppressive therapy.
- Sarcoidosis and disorders causing impaired cell-mediated immunity.
- Biological immunosuppressive therapy.
- Cryptococcosis can occasionally occur in apparently immunocompetent patients, particularly C. gattii infection.
🧾 Clinical Presentation
- Usually subacute, evolving over several days to weeks.
- Headache is very common and may progressively worsen.
- Fever, malaise, lethargy, anorexia and weight loss may occur.
- Altered mental state: confusion, behavioural change, reduced consciousness or cognitive impairment.
- Meningism may be absent, particularly in severely immunocompromised patients.
- Photophobia and neck stiffness are therefore less reliable than in acute bacterial meningitis.
- Cranial neuropathies, visual impairment, hearing loss, seizures or focal neurological deficits may occur.
🧠 Raised Intracranial Pressure
- Raised ICP is one of the most important complications of cryptococcal meningitis.
- Features include severe headache, nausea, vomiting, visual disturbance, diplopia, papilloedema, cranial nerve palsies and impaired consciousness.
- Raised pressure results largely from impaired CSF drainage rather than simply cerebral oedema.
- Opening pressure should therefore be measured whenever LP is performed.
- Clinical deterioration despite appropriate antifungal therapy should always prompt reassessment of ICP.
🌍 Disseminated Disease
- Pulmonary: cough, dyspnoea, fever, nodules, consolidation, cavitation or diffuse infiltrates.
- Skin: papules, nodules or ulcers; classically umbilicated papules that may resemble molluscum contagiosum.
- Cryptococcaemia indicates disseminated infection and should generally be managed as CNS disease.
- Eye, bone, prostate and other organs can also be involved.
🔎 Investigations
- Urgent specialist infection/HIV advice should be sought.
- Baseline investigations include FBC, U&E, creatinine/eGFR, LFTs, CRP and glucose.
- Test for HIV unless already known; if positive obtain CD4 count and HIV viral load.
- Blood cultures should be obtained because cryptococcaemia is common in disseminated disease.
- Serum cryptococcal antigen (CrAg) is highly sensitive in disseminated and CNS infection.
- Chest imaging should be considered to assess pulmonary disease.
🧪 Lumbar Puncture
- LP is central to diagnosis unless temporarily contraindicated.
- Always measure CSF opening pressure with the patient appropriately positioned.
- Send CSF for:
- Cell count and differential.
- Protein and glucose with paired blood glucose.
- Cryptococcal antigen (CrAg).
- Fungal microscopy and culture.
- Additional bacterial, viral or mycobacterial studies according to the differential diagnosis.
🧪 Typical CSF Findings
- Opening pressure: often raised, sometimes markedly.
- White cells: usually lymphocytic, but the cell count may be very low or even normal in advanced immunosuppression.
- Protein: normal or moderately increased.
- Glucose: low or normal.
- A relatively normal CSF profile therefore does not exclude cryptococcal meningitis.
⚠️ Clinical pearl: A patient with advanced HIV can have cryptococcal meningitis with headache, confusion and a very high opening pressure despite only a handful of CSF white cells. A weak inflammatory response may actually indicate profound immunosuppression and high fungal burden.
🦠 Cryptococcal Antigen
- CSF CrAg is the most useful rapid test and has very high sensitivity and specificity.
- Serum CrAg is also highly sensitive in disseminated disease.
- Modern lateral-flow assays provide rapid results and have largely superseded reliance on India ink microscopy.
- A positive serum CrAg in an immunocompromised patient should prompt careful assessment for CNS disease, including LP where appropriate.
🔬 India Ink & Culture
- India ink may demonstrate the characteristic encapsulated budding yeast but is less sensitive than CrAg testing.
- Sensitivity is greatest when the fungal burden is high, such as advanced HIV disease.
- CSF fungal culture confirms viable Cryptococcus and permits species identification.
- Culture is particularly useful when assessing possible microbiological persistence or relapse.
🧠 Brain Imaging
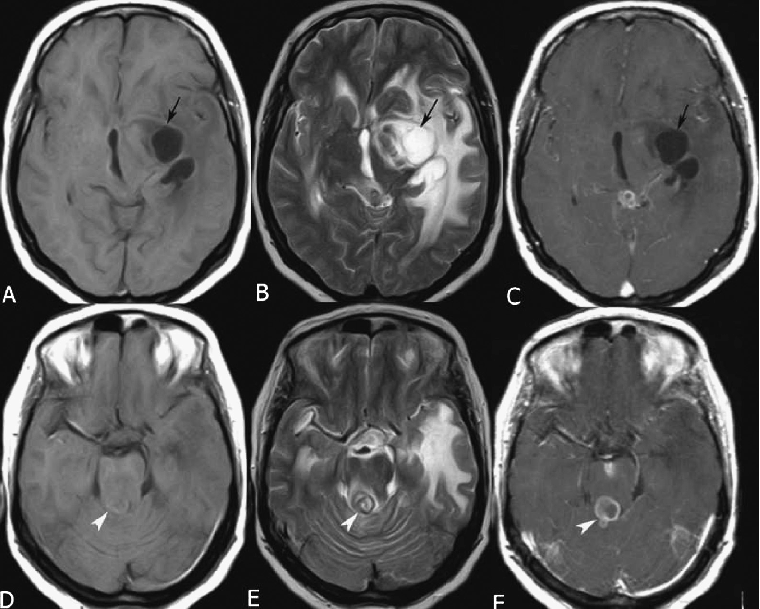
- MRI brain is more sensitive than CT for cryptococcal CNS abnormalities.
- Possible findings include meningeal enhancement, hydrocephalus, infarction, cryptococcomas and dilated perivascular spaces or gelatinous pseudocysts.
- Brain imaging may nevertheless be normal.
- Imaging before LP is appropriate where there are usual clinical concerns about mass effect or obstruction, such as focal neurological deficit, markedly impaired consciousness, new seizures or suspected space-occupying lesion.
- Do not delay essential diagnosis unnecessarily simply because the patient is immunocompromised.
💊 Treatment — UK / Resource-Rich Setting
💊 Preferred induction: In UK/resource-rich practice, cryptococcal meningitis is normally treated initially with IV liposomal amphotericin B plus oral flucytosine, with specialist infection/HIV input.
- Induction therapy:
- Liposomal amphotericin B 3–4 mg/kg IV once daily
- PLUS flucytosine 25 mg/kg orally four times daily (total 100 mg/kg/day).
- Usually continued for a minimum of 2 weeks.
- Longer induction treatment, often 4–6 weeks, may be required in selected patients including CNS cryptococcomas, some C. gattii infections, transplantation or slow microbiological/clinical response.
- Consolidation: fluconazole 400–800 mg once daily for approximately 8 weeks.
- Maintenance / secondary prophylaxis: fluconazole 200 mg once daily, generally for at least 12 months and until adequate immune restoration in HIV.
🌍 WHO HIV Regimen
- WHO guidance for HIV-associated cryptococcal meningitis also supports an alternative simplified induction regimen:
- Single liposomal amphotericin B 10 mg/kg IV dose PLUS
- flucytosine 25 mg/kg QDS for 14 days PLUS
- fluconazole 1200 mg daily for 14 days.
- This regimen has evidence specifically in HIV-associated cryptococcal meningitis and should not simply be extrapolated to non-HIV disease.
🩺 Monitoring During Amphotericin / Flucytosine
- Monitor renal function, potassium and magnesium closely.
- Amphotericin can cause nephrotoxicity, hypokalaemia and hypomagnesaemia.
- Ensure appropriate hydration and replace potassium and magnesium proactively where necessary.
- Monitor FBC because flucytosine may cause bone-marrow suppression.
- Monitor liver function.
- Flucytosine requires dose adjustment in renal impairment; drug-level monitoring may be required according to specialist/local protocols.
- Check for significant drug interactions when fluconazole is introduced.
🚨 Management of Raised ICP
- Opening pressure should be measured at every LP.
- If symptomatic raised ICP is present, particularly with an opening pressure ≥20 cm CSF, perform therapeutic CSF drainage.
- Usually remove approximately 20–30 mL CSF, or sufficient fluid to:
- reduce opening pressure by approximately 50%, or
- achieve a closing pressure ≤20 cm CSF.
- Repeat therapeutic LPs daily if symptoms or raised pressure persist.
- A further scheduled therapeutic LP at approximately 48–72 hours may be beneficial even if the initial pressure was not markedly elevated.
- Persistent raised ICP despite repeated LPs may require lumbar drainage, ventriculostomy or CSF shunting with neurosurgical involvement.
🚨 Do not try to treat cryptococcal raised ICP simply as cerebral oedema. Serial CSF drainage is the key intervention. Mannitol, acetazolamide and routine corticosteroids are not recommended for pressure control and may be harmful.
💊 HIV & Timing of ART
- Do not start ART immediately in newly diagnosed HIV-associated cryptococcal meningitis.
- Starting ART too early increases the risk of severe or fatal cryptococcal immune reconstitution inflammatory syndrome (C-IRIS).
- ART is generally started approximately 4–6 weeks after antifungal therapy begins.
- Timing should be individualised with the HIV/infection team according to clinical response, control of ICP, treatment of other opportunistic infections and, where available, evidence of CSF culture sterility.
🔥 Cryptococcal IRIS
- IRIS may occur after immune recovery following ART or reduction of immunosuppression.
- Patients may develop recurrent headache, fever, lymphadenopathy, raised ICP, neurological deterioration or enlarging inflammatory lesions despite effective antifungal therapy.
- Relapse due to viable organisms must be distinguished from IRIS.
- Repeat LP including opening pressure and fungal culture may therefore be necessary.
🔁 Treatment Failure or Relapse
- Consider:
- Inadequate induction therapy.
- Poor adherence.
- Drug interactions.
- Antifungal resistance, especially fluconazole resistance.
- Persistently raised ICP.
- Cryptococcal IRIS.
- Alternative or additional CNS infection.
- A persistently positive CrAg alone does not prove microbiological relapse; fungal culture demonstrating viable organisms is much more informative.
🧠 Cryptococcoma
- Cryptococcomas are focal granulomatous lesions, more often encountered with C. gattii.
- They may produce seizures, focal neurological signs or mass effect.
- Induction therapy may need extending to 4–6 weeks.
- Neurosurgical intervention is occasionally required for significant mass effect or diagnostic uncertainty.
- Corticosteroids are not routine treatment for cryptococcal meningitis, although specialist-guided steroids may occasionally be considered for large cryptococcomas causing inflammatory mass effect.
📊 Prognosis
- Untreated cryptococcal meningitis is usually fatal.
- Important adverse prognostic features include:
- High fungal burden.
- Markedly raised ICP.
- Reduced level of consciousness.
- Low CSF inflammatory response.
- Cryptococcaemia.
- Delayed or inadequate antifungal treatment.
- Neurological complications include permanent visual loss, hearing impairment, cranial neuropathies, stroke and cognitive impairment.
- Relapse is uncommon when adequate induction, consolidation and maintenance treatment is completed and underlying immune suppression is corrected.
🎓 Key Learning Points
- 🦠 Think of cryptococcal meningitis particularly in advanced HIV or impaired cell-mediated immunity.
- 🧪 CSF CrAg is the key rapid diagnostic investigation.
- 💧 Always measure the CSF opening pressure.
- 🧠 CSF may show only minimal inflammation despite severe infection.
- 💊 UK induction therapy: liposomal amphotericin B + flucytosine.
- 🚨 Raised ICP is treated primarily with repeated therapeutic lumbar puncture.
- 🚫 Avoid routine mannitol, acetazolamide or corticosteroids for ICP.
- ⏱️ In HIV-associated meningitis, delay ART approximately 4–6 weeks rather than starting immediately.
- 🔁 Clinical deterioration after treatment may represent raised ICP, persistent infection, relapse or IRIS — do not assume they are the same process.
| The content on this website is provided for educational and informational purposes only to support exam preparation (e.g., MLA, MRCP, USMLE) and learning. This is NOT medical advice, diagnosis, treatment, or professional guidance. It does not replace consultation with a qualified healthcare professional, official guidelines (e.g., NICE, GMC, BNF), or supervised clinical practice. Always verify information with current, authoritative sources. Makindo and its contributors accept no liability for any reliance on this content, including errors, omissions, or any resulting harm, loss, or consequences. By using this site, you agree to these terms. |
|
|
Categories
- About
- Acute Medicine
- Anaesthetics and Critical Care
- Anatomy
- Anatomy and Physiology
- Biochemistry
- Book
- Cardiology
- Collections
- CompSci
- Crib Sheets
- Critical care
- Dental
- Dermatology
- Differentials
- Drugs
- ENT
- Electrocardiogram
- Embryology
- Emergency Medicine
- Endocrinology
- Ethics
- Foundation Doctors
- GCSE
- Gastroenterology
- General Practice
- Genetics
- Geriatric Medicine
- Geriatrics
- Guidelines
- Haematology
- Hepatology
- Immunology
- Infectious Diseases
- Infographic
- Investigations
- Lists
- MRCP
- Mandatory Training
- Medical Students
- Microbiology
- Nephrology
- Neurology
- Neurosurgery
- Nutrition
- OSCE
- Obstetrics Gynaecology
- Oncology
- Ophthalmology
- Oral Medicine and Dentistry
- Orthopaedics
- Paediatrics
- Palliative
- Palliative Care
- Pathology
- Pharmacology
- Physiology
- Procedures
- Psychiatry
- Public Health
- Radiology
- Respiratory
- Resuscitation
- Revision Topics
- Rheumatology
- Statistics and Research
- Stroke
- Surgery
- Toxicology
- Trauma and Orthopaedics
- USMLE
- Urology
- Vascular Surgery