
| Download the amazing global Makindo app: ✅ Means NICE/National Guidelines 2026 compliant Android | Apple | |
|---|---|
| MEDICAL DISCLAIMER: Educational use only. Not for diagnosis or management. See below for full disclaimer. |
Hypothyroidism ✅
Related Subjects: |Thyroid Cancer |Thyroid Eye Disease |Thyroid Function Tests and antibodies |Thyroid Storm - Thyrotoxic crisis |Thyroid Surgery (Thyroidectomy) |Thyroid nodules |Thyrotoxicosis and Hyperthyroidism |Hypothyroidism
💡 Always start with a lower dose of levothyroxine in the elderly or in patients with angina/heart failure to avoid arrhythmia or myocardial ischaemia.
📖 Introduction
- The thyroid secretes mainly T4; most T3 is produced by peripheral conversion.
- Primary hypothyroidism: thyroid failure → TSH ↑, FT4 ↓.
- Secondary/central hypothyroidism: pituitary/hypothalamic disease → TSH low/normal, FT4 ↓; monitor using FT4 and symptoms.
⚙️ Aetiology
- Primary hypothyroidism: autoimmune (Hashimoto's), post-thyroidectomy/radioiodine/radiotherapy, drugs (lithium, amiodarone), thyroiditis, infiltrative, congenital.
- Secondary/central: pituitary/hypothalamic tumours, surgery, radiotherapy, apoplexy, infiltrative disease.
🧑⚕️ Clinical Features
- General: fatigue, lethargy, weight gain, cold intolerance ❄️
- Neuropsychiatric: poor concentration, low mood, psychomotor slowing 🧠
- GI: constipation 🍽️
- Reproductive: menorrhagia, subfertility 👩🦰
- Skin/hair: dry skin, brittle hair, hair loss, hoarse voice, periorbital puffiness 💇♀️
- Cardio: bradycardia, risk of heart failure, pericardial effusion ❤️
- Neuro exam: slow-relaxing reflexes (“hung-up”), proximal myopathy 💪
- Severe: myxoedema coma ❄️🛌 (rare, emergency)
🆚 Differential Diagnosis
- Depression, chronic fatigue, sleep apnoea 😴
- Anaemia, chronic kidney disease, chronic inflammatory disease
- Central hypothyroidism if FT4 low but TSH not elevated
🔬 Investigations (NICE / UK approach)
- First-line: TSH (and FT4 if TSH abnormal or central hypothyroidism suspected)
- Overt primary: TSH ↑, FT4 ↓
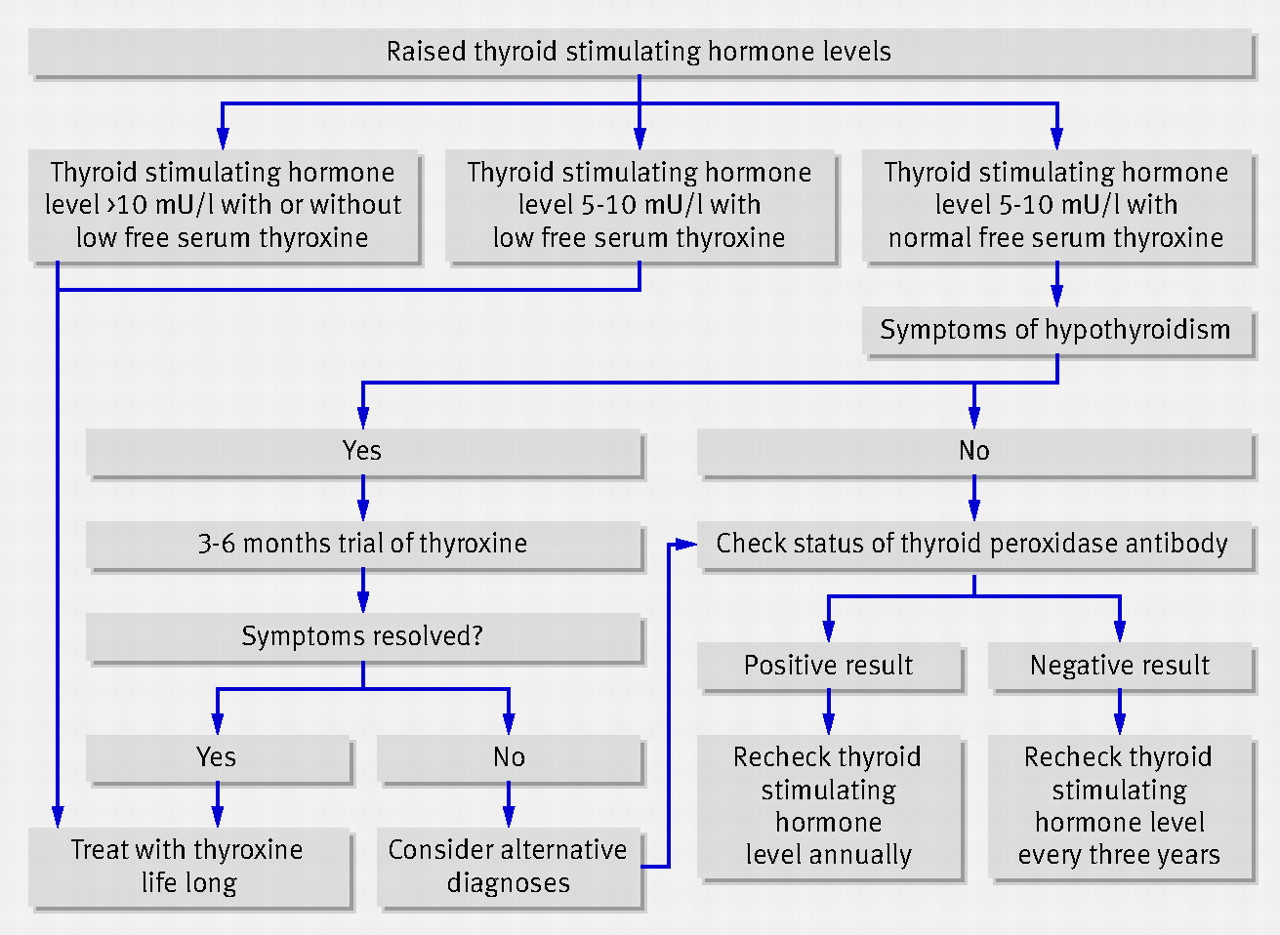
- Subclinical: TSH ↑, FT4 normal → repeat in ~3 months
- Thyroid antibodies: TPO Ab supports autoimmune cause
- Other tests: FBC, lipids, B12/folate if indicated
- Imaging: thyroid ultrasound only if structural concerns
📊 Classification
- Overt primary: TSH ↑, FT4 ↓ → treat with levothyroxine 💊
- Subclinical: TSH ↑, FT4 normal → confirm persistence; treat if TSH ≥10 or symptomatic
- Secondary/central: FT4 ↓, TSH low/normal → monitor and treat guided by FT4 & symptoms
🧪 When to Treat Subclinical Hypothyroidism
- TSH ≥10 mIU/L on 2 occasions → levothyroxine
- TSH 4–10 + symptoms → consider 6-month trial; stop if no benefit
💊 Treatment
- First-line: Levothyroxine (T4) monotherapy
- Starting dose: Adults ~50–100 micrograms OD; elderly/IHD 25–50 micrograms OD → titrate slowly ⬆️
- Take consistently; avoid interaction with iron, calcium, GI disorders
- T3 (liothyronine) rarely used; specialist only
- Central hypothyroidism: titrate using FT4
- Pregnancy: increase dose 25–50%, monitor TSH/FT4 closely 🤰
📈 Monitoring (NICE NG145)
- Primary: TSH every 6–8 weeks until stable → annual
- Persistent symptoms with normal TSH → check FT4
- Central: monitor FT4, TSH unreliable
🚨 Emergencies & Referral
- Myxoedema coma ❄️🛌 → ICU/HDU, IV thyroid hormone + IV hydrocortisone
- Referral: pregnancy, <16y, pituitary disease, difficult TFTs, cardiac disease, drug interactions
📉 ECG Findings
🧪 Treatment Algorithm
🧾 Clinical Cases
Case 1 – Overt primary hypothyroidism 👩🦰
32F, fatigue, weight gain, constipation, cold intolerance. TSH 18, FT4 low, TPO Ab +.
👉 Management: start levothyroxine; recheck TSH ~3 monthly until stable, then annual.
Case 2 – Older patient with IHD ❤️
75M, lethargy, bradycardia, TSH 12, FT4 low.
👉 Management: start low-dose levothyroxine 25–50 micrograms OD, titrate slowly, monitor for angina/arrhythmia.
Case 3 – Subclinical hypothyroidism 🧪
48M, tiredness, TSH 6.8, FT4 normal.
👉 Next step: repeat TFTs in 3–6 months, check TPO Ab.
👉 Management: trial of levothyroxine if symptoms persist; start if TSH ≥10.
📚 References (UK / NICE)
| The content on this website is provided for educational and informational purposes only to support exam preparation (e.g., MLA, MRCP, USMLE) and learning. This is NOT medical advice, diagnosis, treatment, or professional guidance. It does not replace consultation with a qualified healthcare professional, official guidelines (e.g., NICE, GMC, BNF), or supervised clinical practice. Always verify information with current, authoritative sources. Makindo and its contributors accept no liability for any reliance on this content, including errors, omissions, or any resulting harm, loss, or consequences. By using this site, you agree to these terms. |
|
|
Categories
- Acute Medicine
- Anaesthetics and Critical Care
- Cardiology
- Collections
- Dermatology
- Differentials
- Drugs
- Electrocardiogram
- Emergency Medicine
- Endocrinology
- ENT
- Foundation Doctors
- Gastroenterology
- General Practice
- Genetics
- Geriatric Medicine
- Haematology
- Hepatology
- Immunology
- Infectious Diseases
- Investigations
- Microbiology
- Nephrology
- Neurology
- Neurosurgery
- Obstetrics Gynaecology
- Oncology
- Ophthalmology
- Oral Medicine and Dentistry
- OSCE
- Paediatrics
- Palliative
- Pharmacology
- Physiology
- Procedures
- Psychiatry
- Public Health
- Radiology
- Respiratory
- Resuscitation
- Revision Topics
- Rheumatology
- Stroke
- Surgery
- Toxicology
- Trauma and Orthopaedics
- Urology
- Vascular Surgery