
| Download the amazing global Makindo app: ✅ Means NICE/National Guidelines 2026 compliant Android | Apple | |
|---|---|
| MEDICAL DISCLAIMER: Educational use only. Not for diagnosis or management. See below for full disclaimer. |
Upper Gastrointestinal Bleed ✅
Upper gastrointestinal bleeding — first 24 hours
- Recognise / red flags: Haematemesis, melaena or shock may indicate life-threatening haemorrhage. Take an ABC approach, assess perfusion and haemodynamic stability, establish IV access, resuscitate and activate major haemorrhage support when needed.
- Investigate / stratify: Use Glasgow–Blatchford score at first assessment; investigate Hb, coagulation, platelets, U&E, blood group and crossmatch according to severity. Identify cirrhosis/portal hypertension and anticoagulant exposure.
- Initial management: Offer immediate endoscopy after resuscitation to unstable severe bleeds; otherwise offer endoscopy within 24 hours. NICE does not recommend PPI before endoscopy for suspected non-variceal bleeding; use PPI for appropriate endoscopic findings. If variceal bleeding is suspected, give terlipressin and prophylactic antibiotics per specialist pathway.
- Exam pitfall / safety: Do not automatically give oxygen at 15 L/min to every patient: titrate to clinical condition and saturation, while severe shock/critical illness may require initial high-concentration oxygen. Drug reversal and transfusion choices depend on bleeding severity and local protocol.
Source checked 2026-10-30: NICE CG141 plus BTS emergency oxygen guidance. Focused teaching summary only; historical material below has not had a full dose-by-dose review. Use current BNF, local guidelines and specialist advice for individual patients.
Related Subjects: |Upper Gastrointestinal Bleed |Glasgow Blatchford Score |Oesophageal Variceal Bleeding |Dieulafoy Lesion |Mallory-Weiss Tear |Gastric Cancer |Peptic Ulcer Disease |Oesophagogastroduodenoscopy (OGD/EGD) |Hereditary Haemorrhagic Telangiectasia |Hypovolaemic or Haemorrhagic Shock
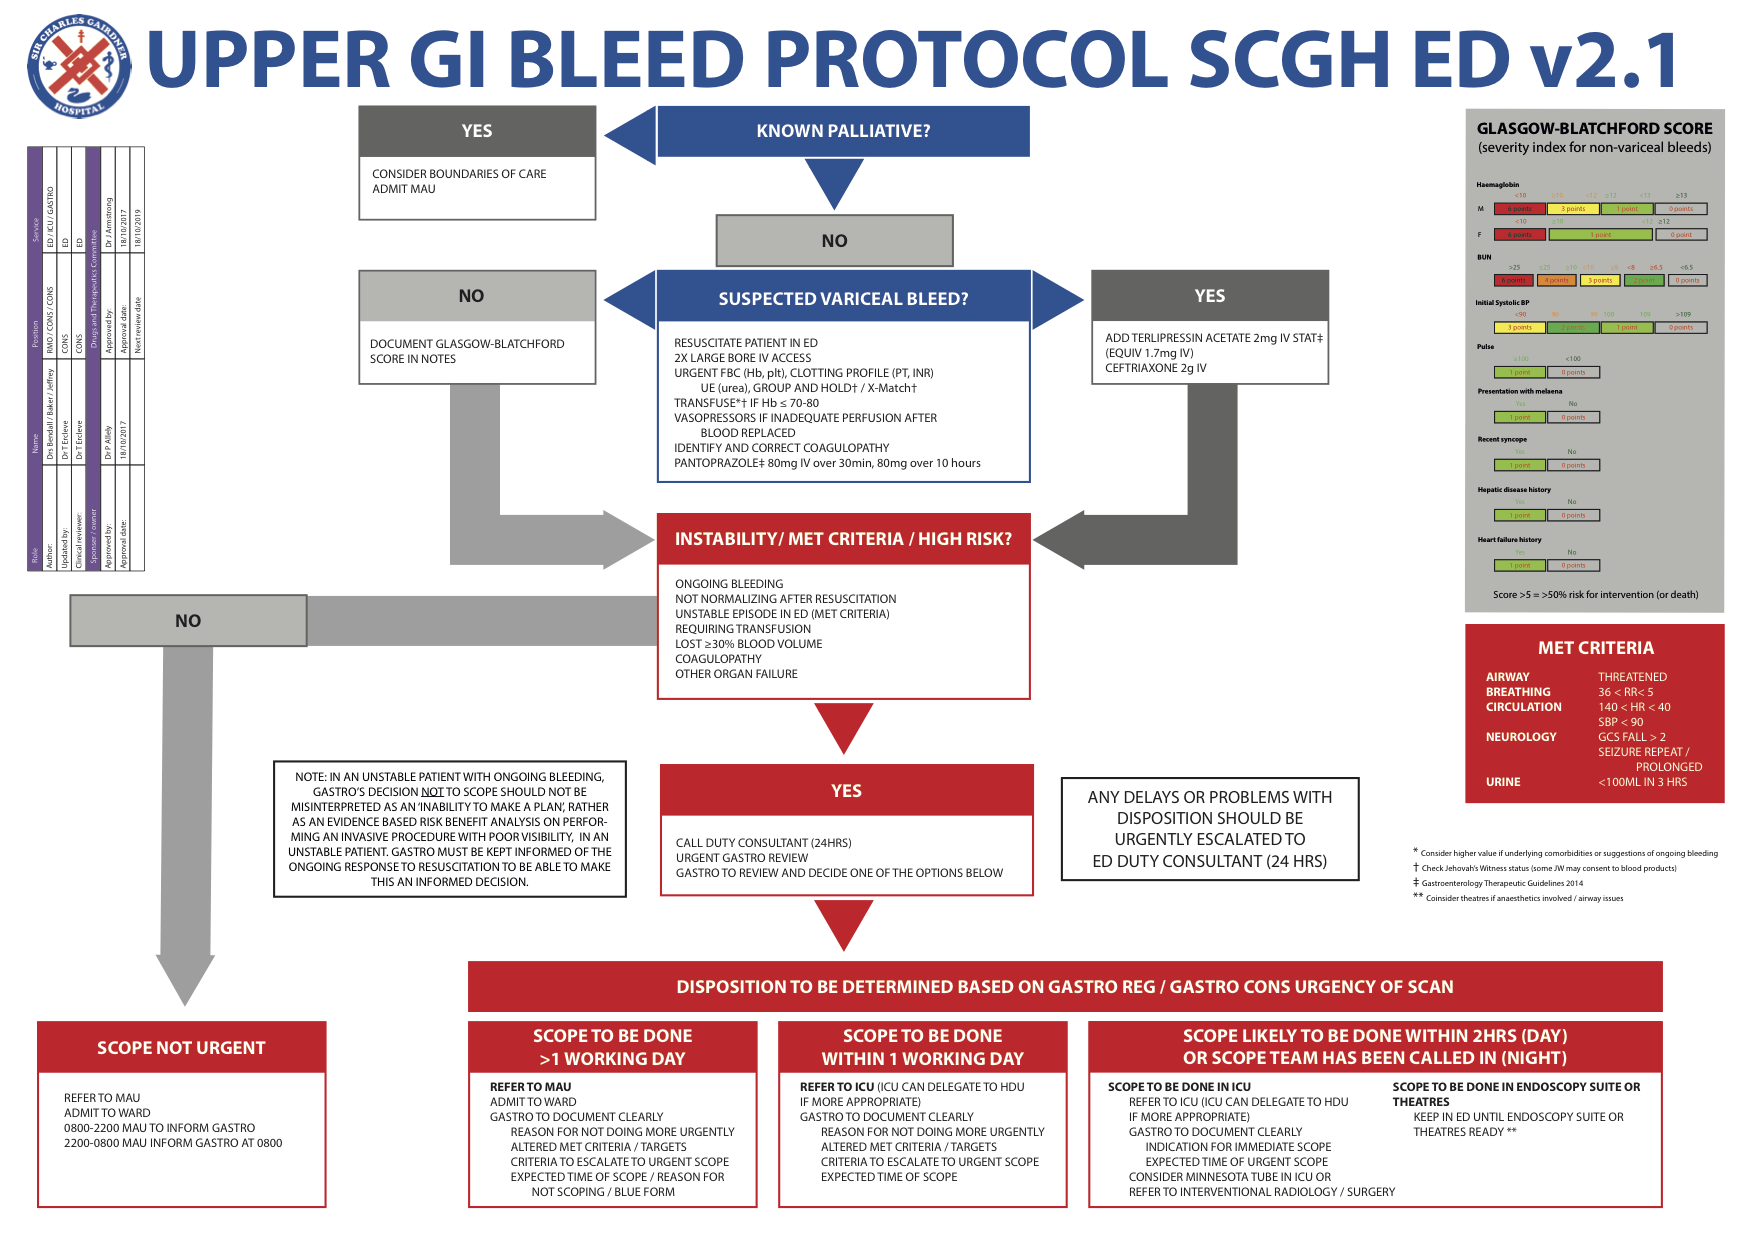
| 🩸 Initial Management of Upper GI Bleed (Shock, Haematemesis, Melaena) |
|---|
|
 ➡️ Endoscopy: Immediately if unstable.
⚠️ All others within 24 h.
If life-threatening bleed despite endoscopy → emergency IR embolisation or surgery.
📊 Incidence
- UK incidence: 80–170 per 100,000/year.
- ~50,000–70,000 hospital admissions/year.
- Mortality ~10% (higher in varices & elderly).
🩺 Clinical Terminology
- Haematemesis: Vomiting fresh blood (UGIB).
- Coffee Grounds: Black vomit due to gastric acid altering blood.
- Melaena: Black, tarry stool (sticky, foul smell).
- Haematochezia: Bright PR blood (usually LGIB, but may be rapid UGIB).
🚨 Major Bleed Signs
- Pulse >100, SBP <100, postural drop >20 mmHg.
- Clammy, cold peripheries, drowsy/confused.
- Haematemesis or melaena on exam.
- Shock disproportionate to Hb drop (Hb may lag early).
⚠️ Risk Factors for Poor Outcome
- Age >60, frailty.
- Persistent melaena/haematemesis.
- Hypotension despite resus.
- Liver disease/varices, malignancy, renal/cardiac failure.
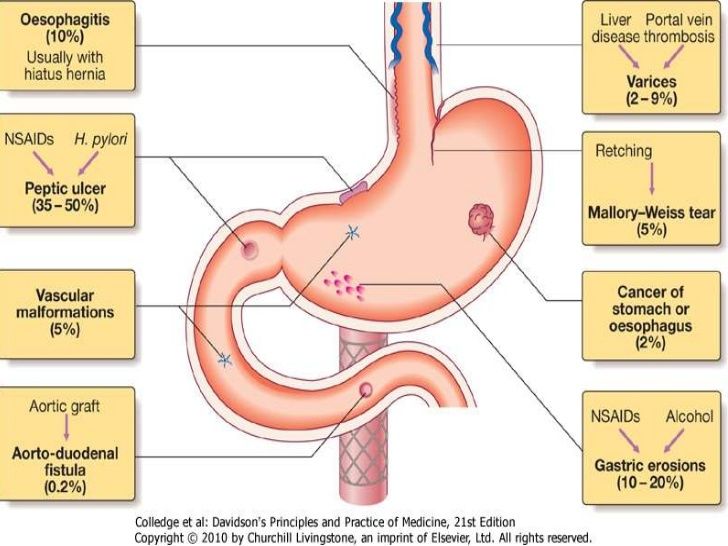
🔎 Causes of UGIB
- Non-variceal (90%): Peptic ulcer disease (50%), gastritis/duodenitis, erosions (NSAIDs, steroids, alcohol, H. pylori), Mallory–Weiss tear, Dieulafoy lesion, vascular ectasia, gastric malignancy.
- Variceal (10%): Oesophageal/gastric varices from portal hypertension (alcoholic cirrhosis, viral hepatitis, NASH).
🧪 Investigations
- Bloods: FBC, U&E, LFTs, clotting, group & save, amylase (exclude pancreatitis).
- ↑ Urea: disproportionate to creatinine (digested blood absorption).
- ECG: exclude ACS (demand ischaemia common).
- Endoscopy: Diagnostic + therapeutic.
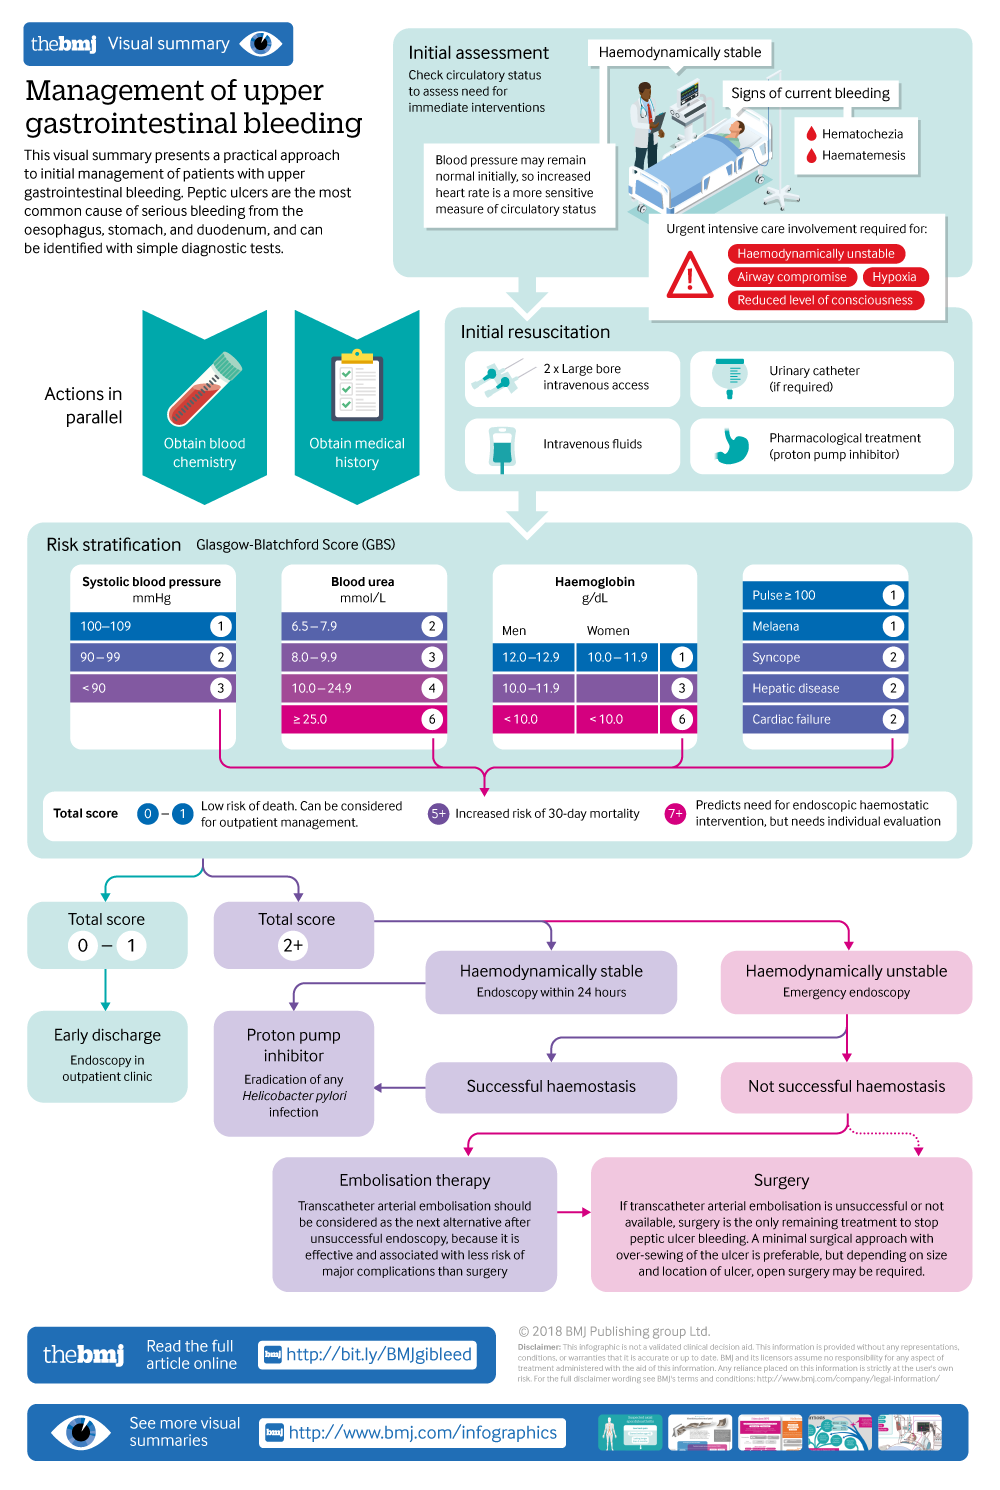
📏 Risk Scores
- Glasgow–Blatchford Score (GBS): at presentation. – 0 = safe discharge if stable. – ≥1 = admit + endoscopy.
- Rockall Score: after endoscopy. – <3 = low risk, >8 = poor prognosis.
💊 Specific Therapies
- Non-variceal bleed: – Endoscopic therapy: adrenaline injection, clips, thermal coagulation. – PPI: Omeprazole 80 mg IV bolus → 8 mg/hr infusion × 72 h. – Long-term: H. pylori eradication (PPI + Amoxicillin 1 g BD + Clarithromycin 500 mg BD × 7 days).
- Variceal bleed: – Terlipressin 2 mg IV every 4 h (max 72 h). – Cefotaxime 1 g IV TDS (SBP prevention). – Endoscopic band ligation (preferred) or sclerotherapy. – If uncontrolled: Sengstaken tube, TIPSS.
- Cirrhotics: Avoid excessive saline → risk of ascites/hyponatraemia. Use blood products carefully.
⚕️ Escalation
- Failure of endoscopy → Interventional Radiology (embolisation).
- Failure of IR → emergency surgery (subtotal gastrectomy / oversewing ulcer).
📚 Exam Pearls
- Painless large-volume UGIB → suspect peptic ulcer or varices.
- Severe pain + bleed → consider perforation or malignancy.
- Melaena vs iron tablets → melaena = black, tarry, sticky, offensive smell.
- Always correct coagulopathy before scope.
- Varices → always combine vasopressin analogue + antibiotics.
📖 References
- NICE UGIB Pathway
- BSG/RCP Joint UGIB Guidance
Additional related clinical topics
Oesophageal Variceal Bleeding
🩸 Oesophageal Variceal Bleeding - Comprehensive Management (Makindo)
⚠️ Medical Emergency: Acute variceal haemorrhage carries a 30–50% mortality per bleed. Management is time-critical: treat on suspicion, not confirmation. Terlipressin + antibiotics + restrictive transfusion should be started immediately. Endoscopy stops the bleed - vasoconstriction buys survival.
📖 Background
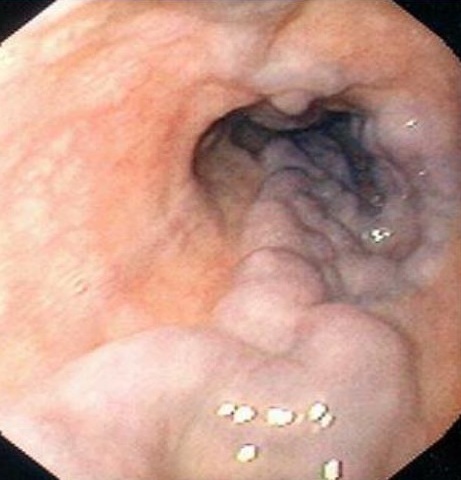
- Oesophageal varices result from portal hypertension, most commonly due to cirrhosis.
- Portal hypertension causes dilation of submucosal oesophageal veins, which rupture under high pressure.
- Bleeding is often brisk, recurrent, and haemodynamically catastrophic.
🧬 Pathophysiology (Why these treatments work)
- Normal portal pressure: < 6 mmHg
- Varices form: ≥ 10 mmHg
- Bleeding risk rises sharply: ≥ 12 mmHg
- Splanchnic vasodilatation (NO-mediated) ↑ portal inflow.
- Vasoactive drugs ↓ portal venous inflow → ↓ variceal wall tension.
🚑 Initial Resuscitation (ABCD first)
- Airway: Early intubation if massive haematemesis, encephalopathy, or shock.
- Breathing: High-flow oxygen.
- Circulation:
- 2 × large-bore IV cannulae.
- Cautious crystalloid boluses.
- Restrictive transfusion: target Hb 7–8 g/dL.
- Avoid over-transfusion (↑ portal pressure → rebleeding).
- Disability: Assess encephalopathy.
🧪 Investigations
- FBC, U&E, LFTs, clotting, lactate.
- Group & crossmatch (≥ 6 units if unstable).
- ABG if shocked or encephalopathic.
- Urgent OGD once stabilised (within 12 hours).
💊 Pharmacological Therapy (Start Immediately)
🔹 Vasoactive Therapy
- Terlipressin (first-line in UK)
- 2 mg IV every 4 hours for first 48 hours
- Then 1 mg IV every 4 hours
- Total duration: 3–5 days (stop after haemostasis achieved)
- Mechanism: Splanchnic vasoconstriction → ↓ portal inflow.
- Contraindications / caution: IHD, severe PVD, uncontrolled hypertension, arrhythmias.
🔹 Antibiotic Prophylaxis (MANDATORY)
- Why: Bacterial translocation increases rebleeding and mortality.
- IV Ceftriaxone (preferred in UK):
- 1 g IV once daily for 7 days
- Especially Child–Pugh B or C
- Alternatives:
- Norfloxacin 400 mg PO BD × 7 days
- Ciprofloxacin 500 mg PO BD × 7 days
🔹 Encephalopathy Prevention
- Lactulose: 20–30 mL PO/NG TDS
- Titrate to 2–3 soft stools/day
🎯 Endoscopic Therapy (Definitive)
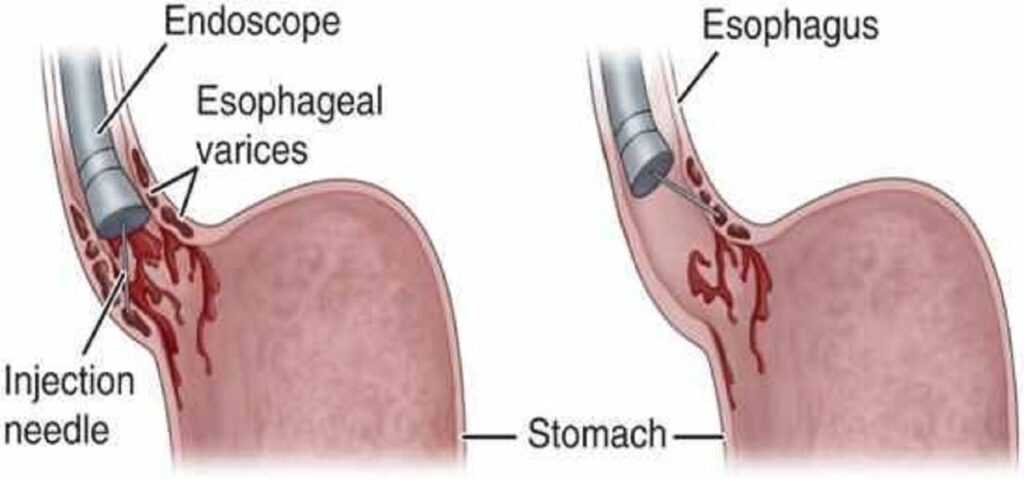
- Endoscopic variceal band ligation - treatment of choice.
- Sclerotherapy if banding not feasible.
- Achieves haemostasis in ~90% when combined with drugs.
🚨 Salvage / Rescue Therapy
- Balloon tamponade (Sengstaken–Blakemore or Minnesota tube)
- Temporary bridge only
- Maximum 24 hours
- High risk: aspiration, oesophageal necrosis
- TIPS (Transjugular Intrahepatic Portosystemic Shunt)
- Indicated for refractory or recurrent bleeding
- Creates low-resistance channel between portal and hepatic veins
- Risk: hepatic encephalopathy
🛡️ Secondary Prophylaxis (After Acute Bleed)
- Non-selective β-blockers
- Propranolol 20–40 mg BD (titrate to HR 55–60)
- Carvedilol 6.25 mg OD → 12.5 mg OD
- Repeat endoscopic band ligation every 2–4 weeks until eradication.
- Optimise cirrhosis management (alcohol abstinence, nutrition, surveillance).
💡 Exam & On-Call Pearls
- Cirrhotic + haematemesis = variceal bleed until proven otherwise.
- Do not wait for endoscopy to start terlipressin and antibiotics.
- Normal Hb early does not exclude massive bleeding.
- Terlipressin is the only vasoactive drug shown to improve survival.
| The content on this website is provided for educational and informational purposes only to support exam preparation (e.g., MLA, MRCP, USMLE) and learning. This is NOT medical advice, diagnosis, treatment, or professional guidance. It does not replace consultation with a qualified healthcare professional, official guidelines (e.g., NICE, GMC, BNF), or supervised clinical practice. Always verify information with current, authoritative sources. Makindo and its contributors accept no liability for any reliance on this content, including errors, omissions, or any resulting harm, loss, or consequences. By using this site, you agree to these terms. |
|
|
Categories
- Acute Medicine
- Anaesthetics and Critical Care
- Cardiology
- Collections
- Dermatology
- Differentials
- Drugs
- Electrocardiogram
- Emergency Medicine
- Endocrinology
- ENT
- Foundation Doctors
- Gastroenterology
- General Practice
- Genetics
- Geriatric Medicine
- Haematology
- Hepatology
- Immunology
- Infectious Diseases
- Investigations
- Microbiology
- Nephrology
- Neurology
- Neurosurgery
- Obstetrics Gynaecology
- Oncology
- Ophthalmology
- Oral Medicine and Dentistry
- OSCE
- Paediatrics
- Palliative
- Pharmacology
- Physiology
- Procedures
- Psychiatry
- Public Health
- Radiology
- Respiratory
- Resuscitation
- Revision Topics
- Rheumatology
- Stroke
- Surgery
- Toxicology
- Trauma and Orthopaedics
- Urology
- Vascular Surgery