Jaundice
Related Subjects:
|Chronic liver disease
|Cirrhosis
|Alkaline phosphatase (ALP)
|Liver Function Tests
|Ascites Assessment and Management
|Budd-Chiari syndrome
|Autoimmune Hepatitis
|Primary Biliary Cirrhosis
|Primary Sclerosing Cholangitis
|Wilson disease
|Hereditary Haemochromatosis
|Alpha-1 Antitrypsin (AAT) deficiency
|Non alcoholic steatohepatitis (NASH)
|Spontaneous Bacterial Peritonitis
|Alcoholism and Alcoholic Liver Disease
|Hepatitis C
|Child-Pugh score
|Gallstone ileus
|Gallstones and biliary colic
|Cholestatic Jaundice
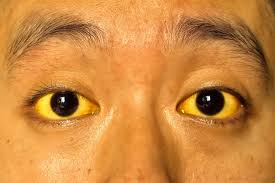
🌟 Jaundice = yellow discolouration of skin, sclera, and mucous membranes due to bilirubin deposition.
👉 Becomes clinically visible when serum bilirubin > 40 µmol/L.
🔎 Always classify by level of pathology: Pre-hepatic (before liver), Hepatic (within liver), Post-hepatic (after liver).
🟥 Pre-Hepatic (Haemolytic) Jaundice
- ⚡ Causes: Increased RBC breakdown → haemolytic anaemia, sickle cell disease, thalassaemia, malaria, autoimmune haemolysis.
- 🩸 Features: Anaemia, pallor, dark urine (urobilinogen ↑), splenomegaly. No pale stools.
- 🔬 Investigations: FBC + reticulocytes (↑), blood smear, LDH ↑, haptoglobin ↓, unconjugated bilirubin ↑, Coombs test if autoimmune.
- 💊 Treatment: Cause-specific (transfusions, folate, hydroxyurea in SCD, splenectomy if severe haemolysis).
🟨 Hepatic (Hepatocellular) Jaundice
- ⚡ Causes: Viral hepatitis (A–E), alcoholic liver disease, NAFLD/NASH, cirrhosis, autoimmune hepatitis, hepatocellular carcinoma.
- 😴 Features: Malaise, anorexia, nausea, dark urine, pale stools, tender hepatomegaly, stigmata of chronic liver disease.
- 🔬 Investigations: LFTs (AST/ALT ↑ > ALP), viral serology, autoimmune screen, ultrasound/CT/MRI, ± liver biopsy.
- 💊 Treatment: Antivirals (HBV, HCV), alcohol cessation, nutrition, transplant if decompensated liver failure.
🟩 Post-Hepatic (Obstructive/Cholestatic) Jaundice
- ⚡ Causes: Gallstones, biliary strictures, pancreatic cancer, cholangiocarcinoma, PSC/PBC.
- 🤢 Features: Dark urine, pale stools, pruritus (bile salts), RUQ/epigastric pain, Courvoisier’s sign (palpable gallbladder in pancreatic cancer).
- 🔬 Investigations: LFTs (ALP & GGT ↑ > ALT), ultrasound (first-line), MRCP/ERCP, CT pancreas if malignancy suspected.
- 💊 Treatment: ERCP ± stenting/stone removal, cholecystectomy, oncological management (Whipple procedure in pancreatic cancer).
🧬 Inherited Jaundice
- ⚡ Conditions: Gilbert’s syndrome (benign, common), Crigler–Najjar syndrome, Dubin–Johnson syndrome.
- 🙂 Features: Intermittent mild jaundice (Gilbert’s) triggered by stress/fasting; usually incidental finding.
- 🔬 Investigations: Bilirubin (unconjugated ↑), normal LFTs, genetic tests if unclear.
- 💊 Treatment: Gilbert’s = reassurance. Crigler–Najjar may need phototherapy, liver transplant if severe.
💊 Drug-Induced Jaundice
- ⚡ Causes: Hepatotoxic drugs (paracetamol overdose, isoniazid, statins, amiodarone, antibiotics like flucloxacillin).
- 🤢 Features: Jaundice, nausea, fatigue, ± hepatitis features (RUQ tenderness, hepatomegaly).
- 🔬 Investigations: LFTs (mixed hepatocellular/cholestatic), careful drug history, ± biopsy if diagnostic uncertainty.
- 💊 Treatment: Stop drug, supportive care, antidotes where available (e.g. N-acetylcysteine for paracetamol).
👶 Neonatal Jaundice
- ⚡ Causes: Physiological (common, 1st week) or pathological (Rh/ABO incompatibility, sepsis, G6PD deficiency, breast milk jaundice).
- 🙂 Features: Yellow skin/sclera, usually within 1st week. Kernicterus risk if bilirubin very high.
- 🔬 Investigations: Serum bilirubin, Coombs test, G6PD assay, blood type/crossmatch.
- 💊 Treatment: Phototherapy, exchange transfusion if severe, treat underlying cause, ensure hydration and feeding support.
📊 Patterns of Jaundice – Quick Comparison
| Type |
Main Cause |
Bilirubin Type |
Key LFT Pattern |
Clinical Features |
| 🟥 Pre-hepatic |
Haemolysis (SCD, thalassaemia) |
Unconjugated ↑ |
LFTs normal |
Anaemia, splenomegaly, dark urine (urobilinogen ↑), no pale stools |
| 🟨 Hepatic |
Hepatitis, cirrhosis |
Mixed ↑ |
ALT/AST ↑ > ALP |
Malaise, tender hepatomegaly, stigmata of CLD, dark urine + pale stools |
| 🟩 Post-hepatic |
Gallstones, pancreatic cancer |
Conjugated ↑ |
ALP & GGT ↑ > ALT |
Pale stools, dark urine, pruritus, RUQ pain, Courvoisier’s sign |
💡 Clinical Pearls
- 🌟 Gilbert’s syndrome is very common - mild intermittent jaundice with normal LFTs.
- 🟩 Post-hepatic jaundice + painless mass + palpable gallbladder = think pancreatic head cancer.
- ⚡ Always distinguish conjugated vs unconjugated bilirubin in workup.
- 👶 In neonates, prolonged jaundice (>14 days) = always pathological → investigate.
- 🧪 First-line imaging for obstructive jaundice = ultrasound (look for dilated ducts, gallstones, masses).
Cases - Jaundice
- Case 1 - Pre-hepatic (haemolysis) 🩸: A 25-year-old man with sickle cell disease presents with scleral icterus, dark urine, and mild splenomegaly. Bloods: raised unconjugated bilirubin, reticulocytosis, low haptoglobin. Diagnosis: haemolytic jaundice. Managed by optimising sickle care and transfusion if needed.
- Case 2 - Viral hepatitis (hepatocellular) 🦠: A 22-year-old student returns from travel with malaise, anorexia, and right upper quadrant pain. Exam: tender hepatomegaly, jaundice. Bloods: ALT 1500, AST 1300, bilirubin 95 µmol/L. Hepatitis A IgM positive. Diagnosis: acute viral hepatitis A causing jaundice. Managed with supportive care.
- Case 3 - Alcoholic hepatitis 🍺: A 46-year-old man with chronic alcohol misuse presents with jaundice, fever, and right upper quadrant tenderness. Bloods: bilirubin 180 µmol/L, AST 180, ALT 70 (AST:ALT >2). Maddrey score elevated. Diagnosis: alcoholic hepatitis with jaundice. Managed with alcohol withdrawal support, corticosteroids (if severe), and nutritional therapy.
- Case 4 - Obstructive jaundice (malignancy) 🎗️: A 70-year-old man presents with painless jaundice, pruritus, and pale stools. Exam: palpable gallbladder (Courvoisier’s sign). LFTs: cholestatic pattern (ALP 720, bilirubin 230). Ultrasound: dilated bile ducts, pancreatic head mass. Diagnosis: obstructive jaundice from pancreatic cancer. Managed with biliary stenting and oncology referral.
- Case 5 - Gallstone obstruction 🪨: A 45-year-old woman presents with jaundice, fever, and right upper quadrant pain. Exam: positive Murphy’s sign. LFTs: cholestatic pattern. Ultrasound: gallstones and common bile duct dilation. Diagnosis: choledocholithiasis with obstructive jaundice. Managed with IV antibiotics and ERCP stone removal.
Teaching Point 🩺: Jaundice results from raised bilirubin due to pre-hepatic (haemolysis), hepatic (hepatitis, cirrhosis), or post-hepatic (biliary obstruction) causes. Work-up includes LFT pattern, haemolysis screen, viral serology, and imaging of the biliary tree. Always ask about alcohol, drugs, travel, and family history.
Additional related clinical topics
OSCE Jaundice
🟡 Clinical Pearl: Always be ready to suggest differentials and investigations.
First-line tests 👉 LFTs, bilirubin, FBC.
Imaging 👉 Abdominal ultrasound.
In older patients with pronounced jaundice:
– Painful jaundice → gallstone in CBD (choledocholithiasis).
– Painless jaundice → cancer of head of pancreas (classic exam favourite).
🛠️ Management: ERCP for stone removal or stenting for obstruction.
👋 Introduction
- 🧼 Hand Hygiene: Wash your hands before beginning.
- 🙂 Patient Introduction: Introduce yourself, check name & DOB, explain the exam.
- 📝 Consent & Privacy: Gain consent, ensure good lighting & dignity with drapes.
- 📖 Context: Jaundice = yellow discoloration of skin/sclera from raised bilirubin due to liver, biliary, or haemolytic pathology.
🧰 Equipment Needed
- Gloves
- Good natural/artificial light (pen torch if needed)
- Towel or drape for dignity
- Stethoscope (if extending into abdominal exam)
📚 Background Information
| Category |
Cause |
Mechanism |
Key Features |
| Pre-hepatic |
Haemolytic Anaemia |
↑ RBC breakdown → unconjugated bilirubin |
Anaemia, dark urine, splenomegaly, ↑ reticulocytes |
| Hepatic |
Viral Hepatitis |
Hepatocyte injury → impaired conjugation |
RUQ pain, malaise, jaundice, ↑ ALT/AST |
| Alcoholic Hepatitis |
Alcohol-induced hepatocellular damage |
Tender hepatomegaly, AST:ALT > 2, jaundice |
| Drug-Induced |
Medication hepatotoxicity |
Jaundice + systemic features, temporal drug link |
| Gilbert’s Syndrome |
UGT deficiency → mild unconjugated rise |
Intermittent jaundice triggered by stress/fasting |
| Post-hepatic |
Choledocholithiasis |
CBD obstruction by gallstone |
Dark urine, pale stools, pruritus, biliary colic |
| Pancreatic Ca (Head) |
Tumour compressing CBD |
Painless jaundice, weight loss, Courvoisier’s sign |
| Cholangiocarcinoma |
Bile duct malignancy |
Progressive jaundice, itching, pale stools |
🪜 Examination Steps
- 👀 General Inspection:
- Look for cachexia (malignancy/alcoholism), jaundice in face/skin, spider naevi, palmar erythema, dilated veins.
- Check hands for clubbing, nails for leukonychia (chronic liver disease).
- 👁️ Eye Examination: Inspect sclera for yellow discoloration (scleral icterus) – usually seen before skin changes.
- 👄 Mucous Membranes: Look under tongue & inner cheeks for yellowing – useful in darker skin tones.
- 🩺 Focused Abdomen:
- Palpate RUQ → hepatomegaly/tenderness.
- Percuss liver span, check for splenomegaly/ascites.
- Cancer → hard irregular liver, Ascites → advanced cirrhosis/obstruction.
- 📋 History Adjunct:
- Urine colour (dark) + stool colour (pale) = obstructive.
- RUQ pain/fever = cholangitis/stone.
- Painless jaundice + weight loss = pancreatic malignancy.
✅ Closure
- Thank patient, allow to redress, maintain dignity.
- Explain findings: “You appear jaundiced - we would need to do blood tests and imaging to find the cause.”
- Wash hands, document findings clearly.
⭐ Key OSCE Points
- Always examine in good light.
- Look at sclera and mucous membranes first (early jaundice signs).
- Systematic: General → Eyes → Skin → Mucosa → Abdomen.
- Be ready to suggest investigations + management (LFTs, US, ERCP).
🚫 Common Pitfalls
- Examining in poor light → missing subtle icterus.
- Not checking mucous membranes (can miss early jaundice).
- Rushing → skipping abdominal exam.
- Not correlating with systemic signs of liver disease.
📚 References
