Acute Bacterial Meningitis (Adults) ✅
Suspected bacterial meningitis — sampling without delay
- Recognise / red flags: Fever, headache, neck stiffness and altered mental state may be incomplete, especially in older people. Meningococcal sepsis may present with shock or purpura and needs an immediate sepsis response.
- Investigate / stratify: Take blood cultures and perform lumbar puncture before antibiotics IF safe and without causing clinically significant delay. CT is not a routine prerequisite for LP: investigate selected raised-ICP/focal-neurology red flags, and stabilise shock, airway or seizures first.
- Initial management: Give IV antibiotics as soon as meningitis is suspected, within 1 hour of arrival in hospital. NICE favours ceftriaxone before organism identification, adding amoxicillin for Listeria risk factors, with infectious-disease input. Give IV dexamethasone with or before the first antibiotic dose when indicated, but never delay antibiotics to administer it.
- Exam pitfall / safety: The older summary “antibiotics must always precede LP” is incorrect for stable patients when LP can be done safely and promptly. Do not routinely add aciclovir without strong suspicion of HSV encephalitis.
Source checked 2026-10-30: NICE NG240 (March 2024). Focused teaching summary only; historical material below has not had a full dose-by-dose review. Use current BNF, local guidelines and specialist advice for individual patients.
Related Subjects:
|Adrenal Physiology
|Addisons Disease
|Lumbar Puncture
|CSF Interpretation
💉 Immediate Action: For strongly suspected meningococcal disease outside hospital, arrange emergency transfer and give IV/IM ceftriaxone or benzylpenicillin as soon as possible without delaying transfer. For other strongly suspected bacterial meningitis, consider pre-hospital antibiotics when a clinically significant transfer delay is expected. In hospital, take blood samples and perform lumbar puncture before antibiotics if safe and without a clinically significant delay; otherwise start IV antibiotics without waiting for LP, within 1 hour of arrival. Early therapy significantly reduces mortality.

🚑 Initial Management Summary (Adult Bacterial Meningitis)
- 🫁 ABC stabilization: Airway, breathing, circulation; monitor vitals; admit for LP. Perform CT first if signs of SOL, papilloedema, or focal deficits.
- 🧪 Take blood cultures before antibiotics if feasible; CSF culture after LP.
- 💊 Empirical therapy (UK NICE / BNF): Ceftriaxone 2g BD (NICE NG240 first choice; cefotaxime 2g QDS if ceftriaxone unsuitable).
- ➕ Add IV Amoxicillin if Listeria risk factors (age ≥60, pregnancy, immunocompromised).
- ➕ Add Vancomycin if penicillin-resistant pneumococcus or post-neurosurgical meningitis suspected.
- ➕ Add IV Aciclovir if viral encephalitis suspected (HSV).
- 💊 Dexamethasone 0.15 mg/kg IV (≈10 mg) every 6h for 4 days – ideally before or with first antibiotic dose.
- 🏥 Supportive care: fluids, oxygen, seizure management, monitoring for shock.
📖 Key Points
- Untreated bacterial meningitis mortality: 70–100%.
- Base treatment on clinical suspicion – do not delay for LP/CT.
- Atypical presentations common in elderly, immunocompromised, or young children.
- Early recognition and intervention drastically reduce mortality and long-term complications.
🧬 Aetiology & Pathophysiology
- Bacteria invade subarachnoid space → intense inflammation → cerebral oedema, thrombophlebitis, raised ICP.
- Common organisms: Streptococcus pneumoniae, Neisseria meningitidis, Haemophilus influenzae.
- Pathogenesis: nasopharyngeal colonisation → bloodstream invasion → blood-brain barrier penetration → purulent exudate.
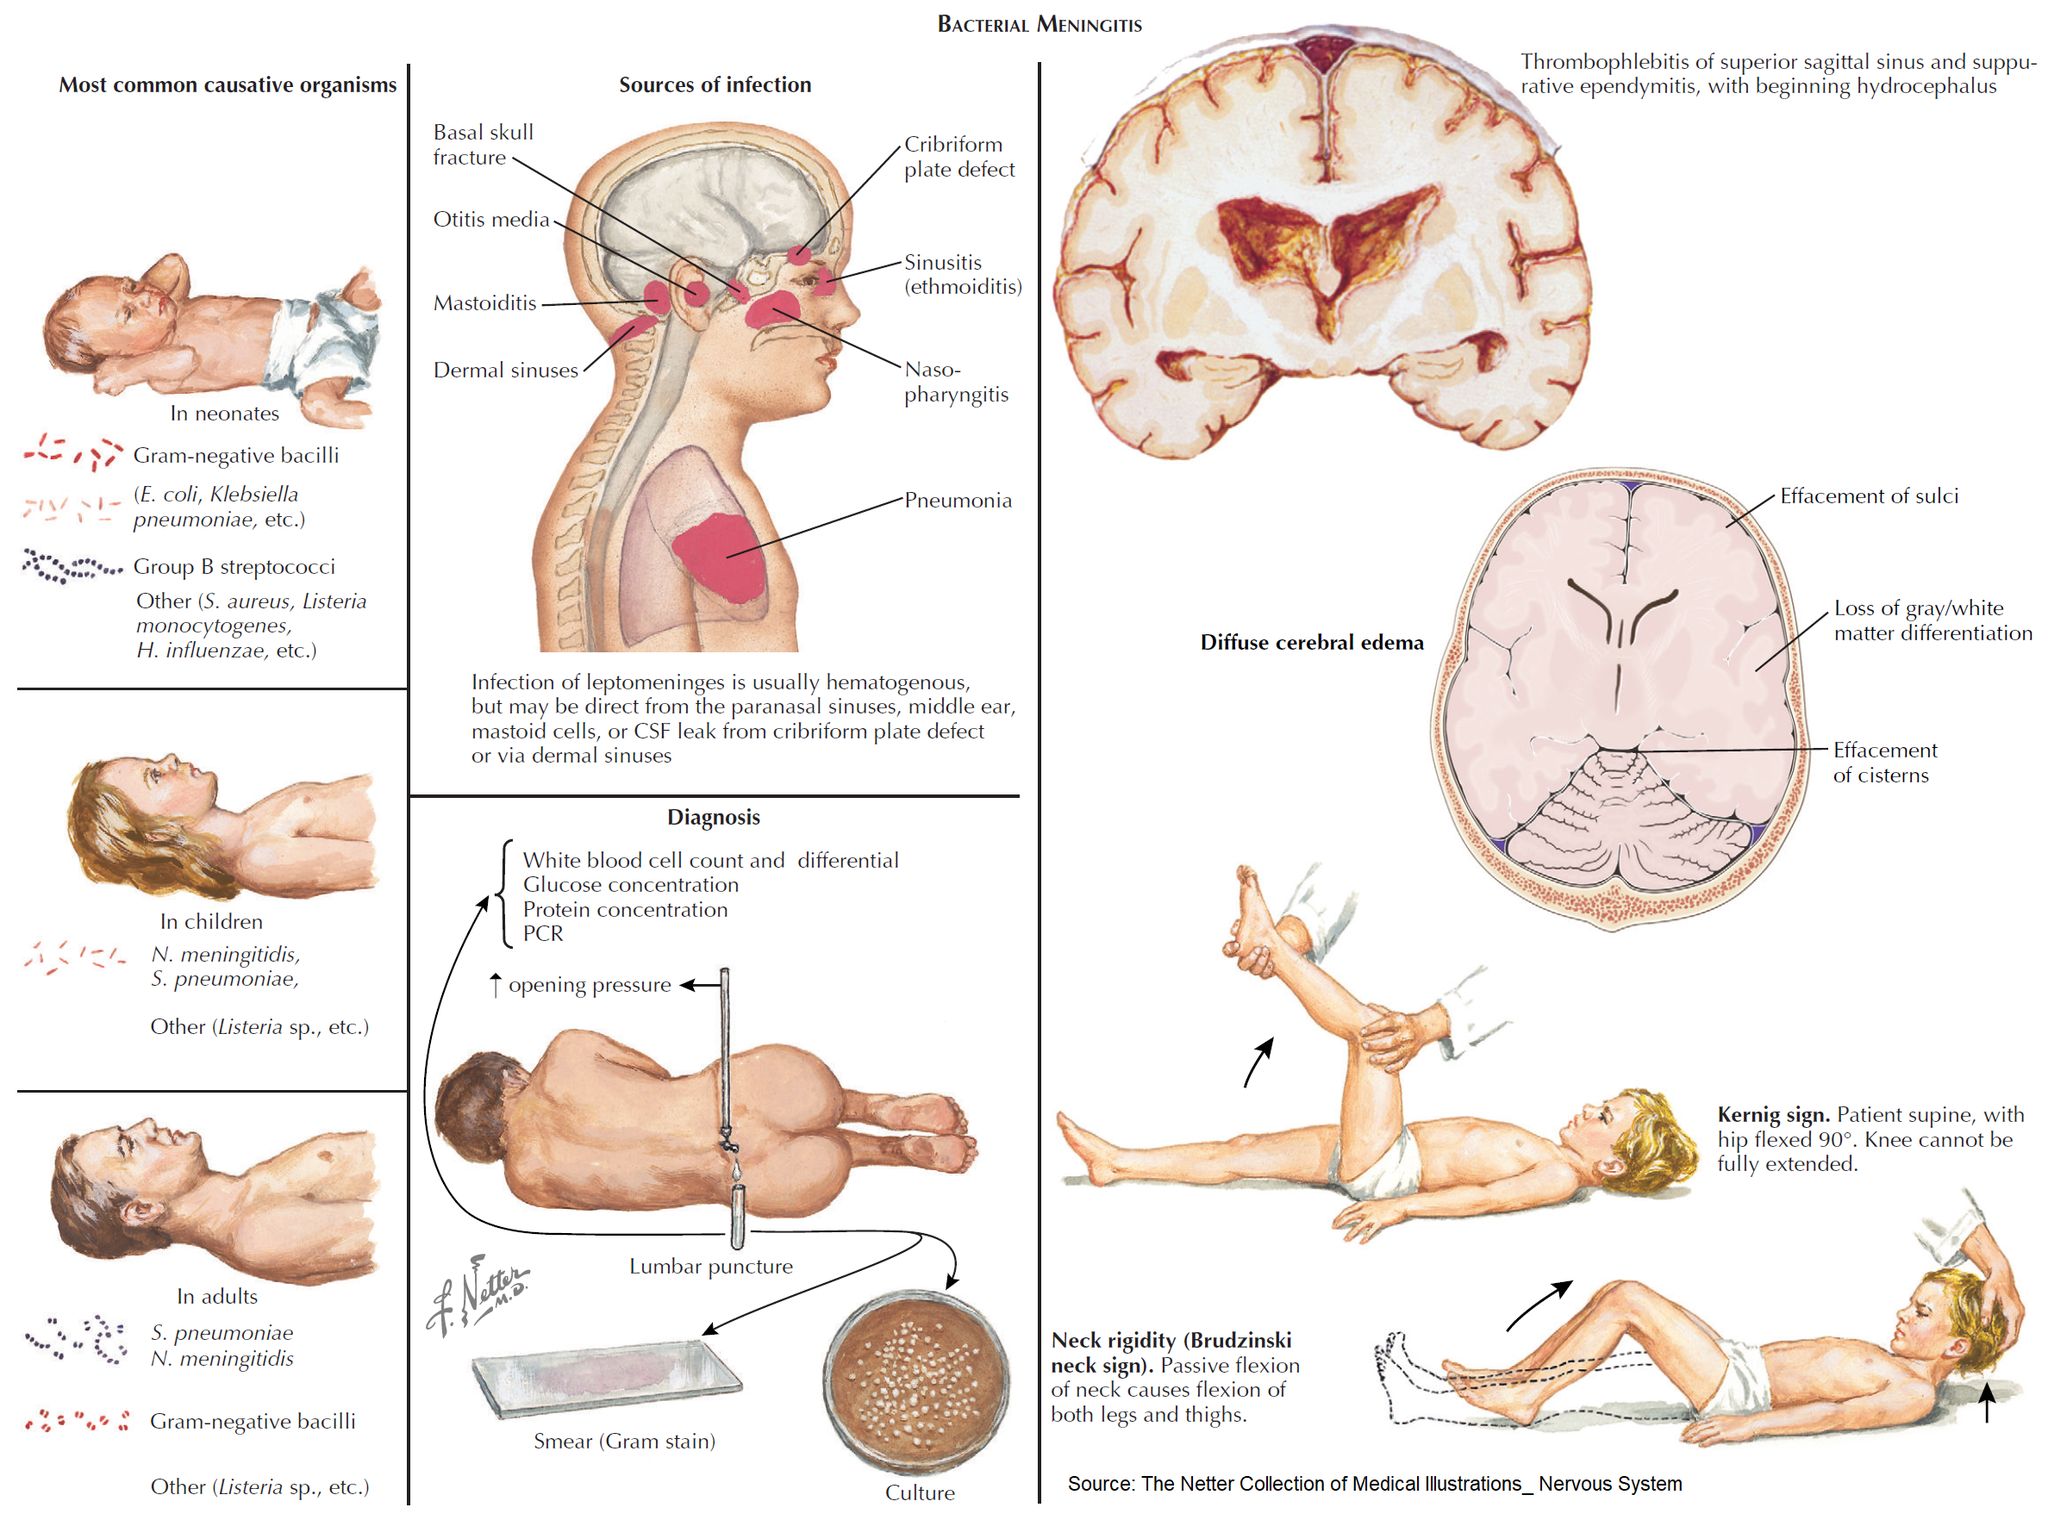
🦠 Common Organisms & Empirical Therapy
| Organism |
Clinical Clues |
Empirical Antibiotic |
| Streptococcus pneumoniae |
Adults, alcoholics, post-splenectomy, basal skull fracture |
Ceftriaxone/Cefotaxime ± Vancomycin |
| Neisseria meningitidis |
Adolescents/young adults, purpuric/petechial rash, complement deficiency |
Ceftriaxone or Cefotaxime |
| Haemophilus influenzae |
Rare due to vaccination; consider in unvaccinated adults |
Cefotaxime/Ceftriaxone |
| Listeria monocytogenes |
Neonates, elderly, pregnancy, immunocompromised |
Amoxicillin ± Gentamicin |
| Staphylococcus aureus |
Post-neurosurgery, hospital-acquired |
Vancomycin |
| Cryptococcus |
Immunocompromised (HIV/AIDS) |
Amphotericin B + Flucytosine → Fluconazole |
🧾 Clinical Presentation
- Classic triad: Fever, Neck stiffness, Altered mental status (~45% cases).
- Other features: headache, photophobia, vomiting, seizures, rash (meningococcal).
- Elderly/immunocompromised: may present subtly; meningism often absent.
- Advanced: cranial nerve palsies (VI common), papilloedema, coma.
⚠️ Complications
- Seizures, stroke, SIADH / hyponatraemia.
- Hydrocephalus, herniation, cerebral abscess.
- Septic shock, DIC (especially meningococcal).
🔎 Investigations
- Bloods: FBC, U&E, CRP, glucose, cultures.
- CT head: if reduced GCS, focal neurology, papilloedema.
- CSF (LP, after imaging if needed):
- Bacterial: high neutrophils, ↑protein, ↓glucose ratio <0.4.
- Viral: lymphocytes, normal glucose, mild ↑protein.
- TB/fungal: lymphocytes, very low glucose, very high protein.
💊 Management Principles
- Give immediate antibiotics – do not wait for LP or imaging.
- Dexamethasone ideally before or with first antibiotic dose to reduce neurological complications.
- Supportive: IV fluids, oxygen, seizure control.
- Early referral to neurosurgery / ID if complications: abscess, hydrocephalus, raised ICP.
👨👩👧 Close Contact Prophylaxis
- Rifampicin 600 mg PO BD × 2 days.
- Alternatives: Ciprofloxacin 500 mg PO single dose, or Ceftriaxone 250 mg IM single dose.
- Follow local Public Health / PHE guidance.
📝 Student / Exam Tips
- ⚡ “Red flag” = sudden fever + neck stiffness + altered mental status → treat as bacterial meningitis until proven otherwise.
- 💉 Antibiotics do not wait for LP if high suspicion.
- 🧪 Blood cultures ideally before antibiotics.
- 💊 Dexamethasone reduces risk of hearing loss and neurological sequelae in pneumococcal meningitis.
- 🚨 Know common organisms by age/risk factors; Listeria in elderly/pregnant/immunocompromised.
- 🖼 Imaging (CT) is required if reduced GCS, focal neuro signs, or papilloedema.
- 👨👩👧 Close contacts need prophylaxis; important in exams to mention.
📚 References / Guidelines
